p.10 抽出テキスト
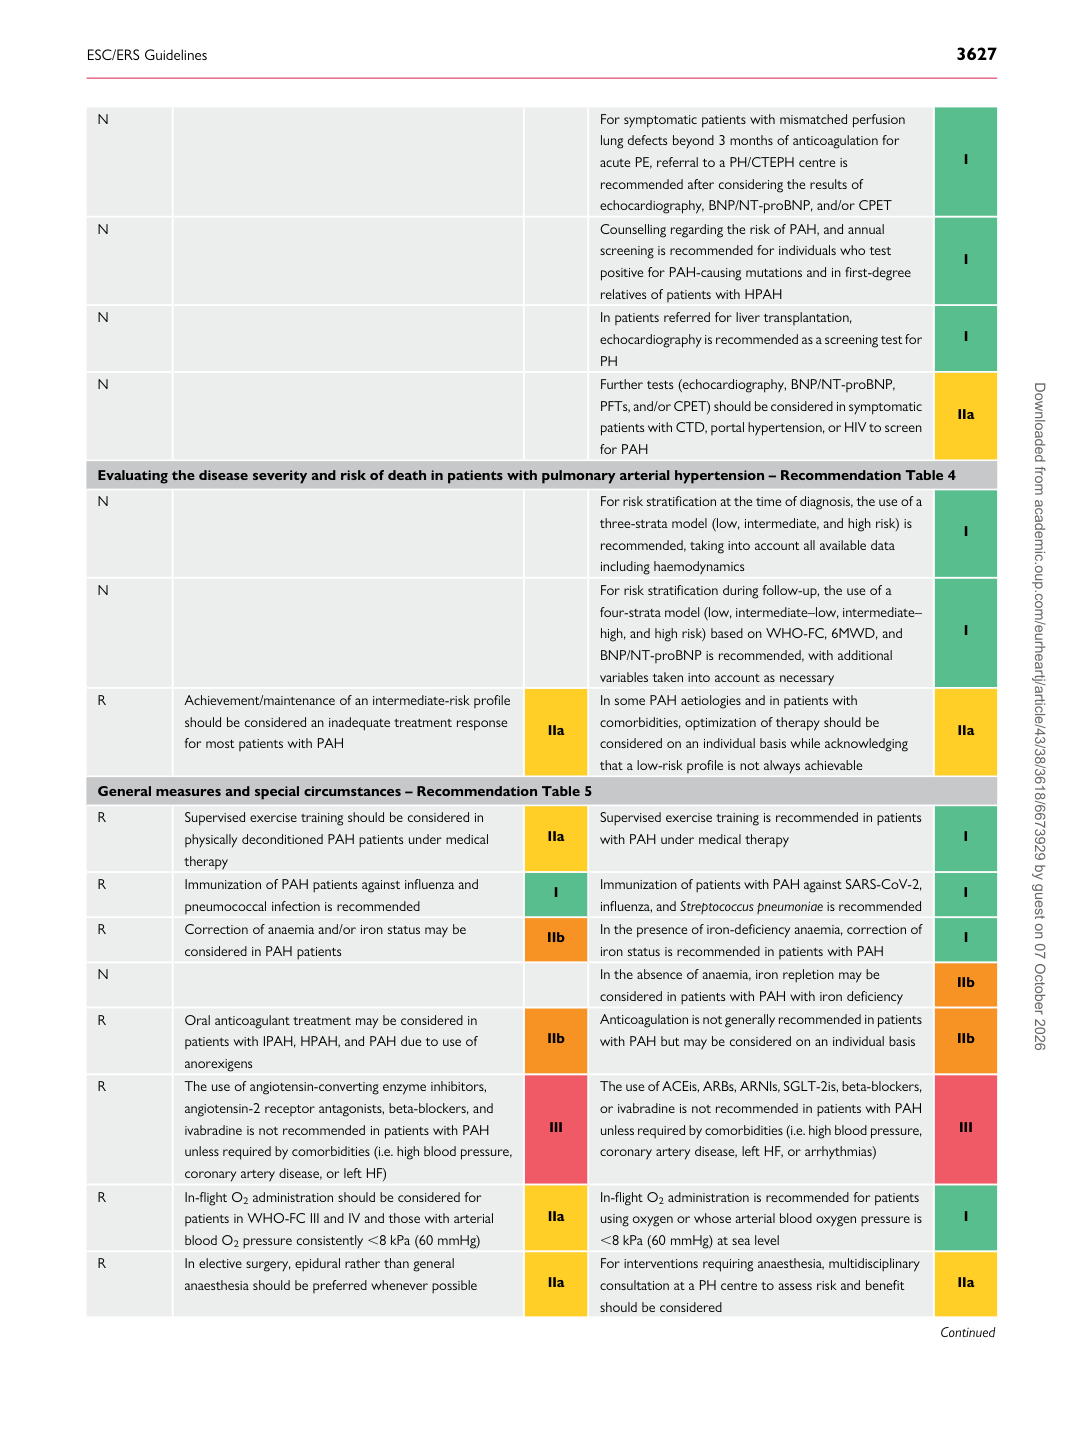
N For symptomatic patients with mismatched perfusion

lung defects beyond 3 months of anticoagulation for acute PE, referral to a PH/CTEPH centre is recommended after considering the results of echocardiography, BNP/NT-proBNP, and/or CPET I

N Counselling regarding the risk of PAH, and annual

screening is recommended for individuals who test positive for PAH-causing mutations and in first-degree relatives of patients with HPAH I

N In patients referred for liver transplantation, echocardiography is recommended as a screening test for

PH I

N Further tests (echocardiography, BNP/NT-proBNP,

PFTs, and/or CPET) should be considered in symptomatic patients with CTD, portal hypertension, or HIV to screen for PAH IIa

Evaluating the disease severity and risk of death in patients with pulmonary arterial hypertension – Recommendation Table 4 N For risk stratification at the time of diagnosis, the use of a three-strata model (low, intermediate, and high risk) is

recommended, taking into account all available data including haemodynamics I

N For risk stratification during follow-up, the use of a

four-strata model (low, intermediate–low, intermediate– high, and high risk) based on WHO-FC, 6MWD, and BNP/NT-proBNP is recommended, with additional variables taken into account as necessary I

R Achievement/maintenance of an intermediate-risk profile

should be considered an inadequate treatment response for most patients with PAH IIa In some PAH aetiologies and in patients with

comorbidities, optimization of therapy should be considered on an individual basis while acknowledging that a low-risk profile is not always achievable IIa

General measures and special circumstances – Recommendation Table 5 R Supervised exercise training should be considered in

physically deconditioned PAH patients under medical therapy IIa Supervised exercise training is recommended in patients

with PAH under medical therapy I

R Immunization of PAH patients against influenza and

pneumococcal infection is recommended I Immunization of patients with PAH against SARS-CoV-2,

influenza, and Streptococcus pneumoniae is recommended I

R Correction of anaemia and/or iron status may be

considered in PAH patients IIb In the presence of iron-deficiency anaemia, correction of

iron status is recommended in patients with PAH I

N In the absence of anaemia, iron repletion may be

considered in patients with PAH with iron deficiency IIb

R Oral anticoagulant treatment may be considered in

patients with IPAH, HPAH, and PAH due to use of anorexigens IIb Anticoagulation is not generally recommended in patients

with PAH but may be considered on an individual basis IIb

R The use of angiotensin-converting enzyme inhibitors, angiotensin-2 receptor antagonists, beta-blockers, and

ivabradine is not recommended in patients with PAH unless required by comorbidities (i.e. high blood pressure, coronary artery disease, or left HF) III The use of ACEis, ARBs, ARNIs, SGLT-2is, beta-blockers, or ivabradine is not recommended in patients with PAH

unless required by comorbidities (i.e. high blood pressure, coronary artery disease, left HF, or arrhythmias) III

R In-flight O2 administration should be considered for patients in WHO-FC III and IV and those with arterial

blood O2 pressure consistently ,8 kPa (60 mmHg) IIa In-flight O2 administration is recommended for patients using oxygen or whose arterial blood oxygen pressure is

,8 kPa (60 mmHg) at sea level I

R In elective surgery, epidural rather than general

anaesthesia should be preferred whenever possible IIa For interventions requiring anaesthesia, multidisciplinary

consultation at a PH centre to assess risk and benefit should be considered IIa

Continued Downloaded from academic.oup.com/eurheartj/article/43/38/3618/6673929 by guest on 07 October 2026