p.79 抽出テキスト
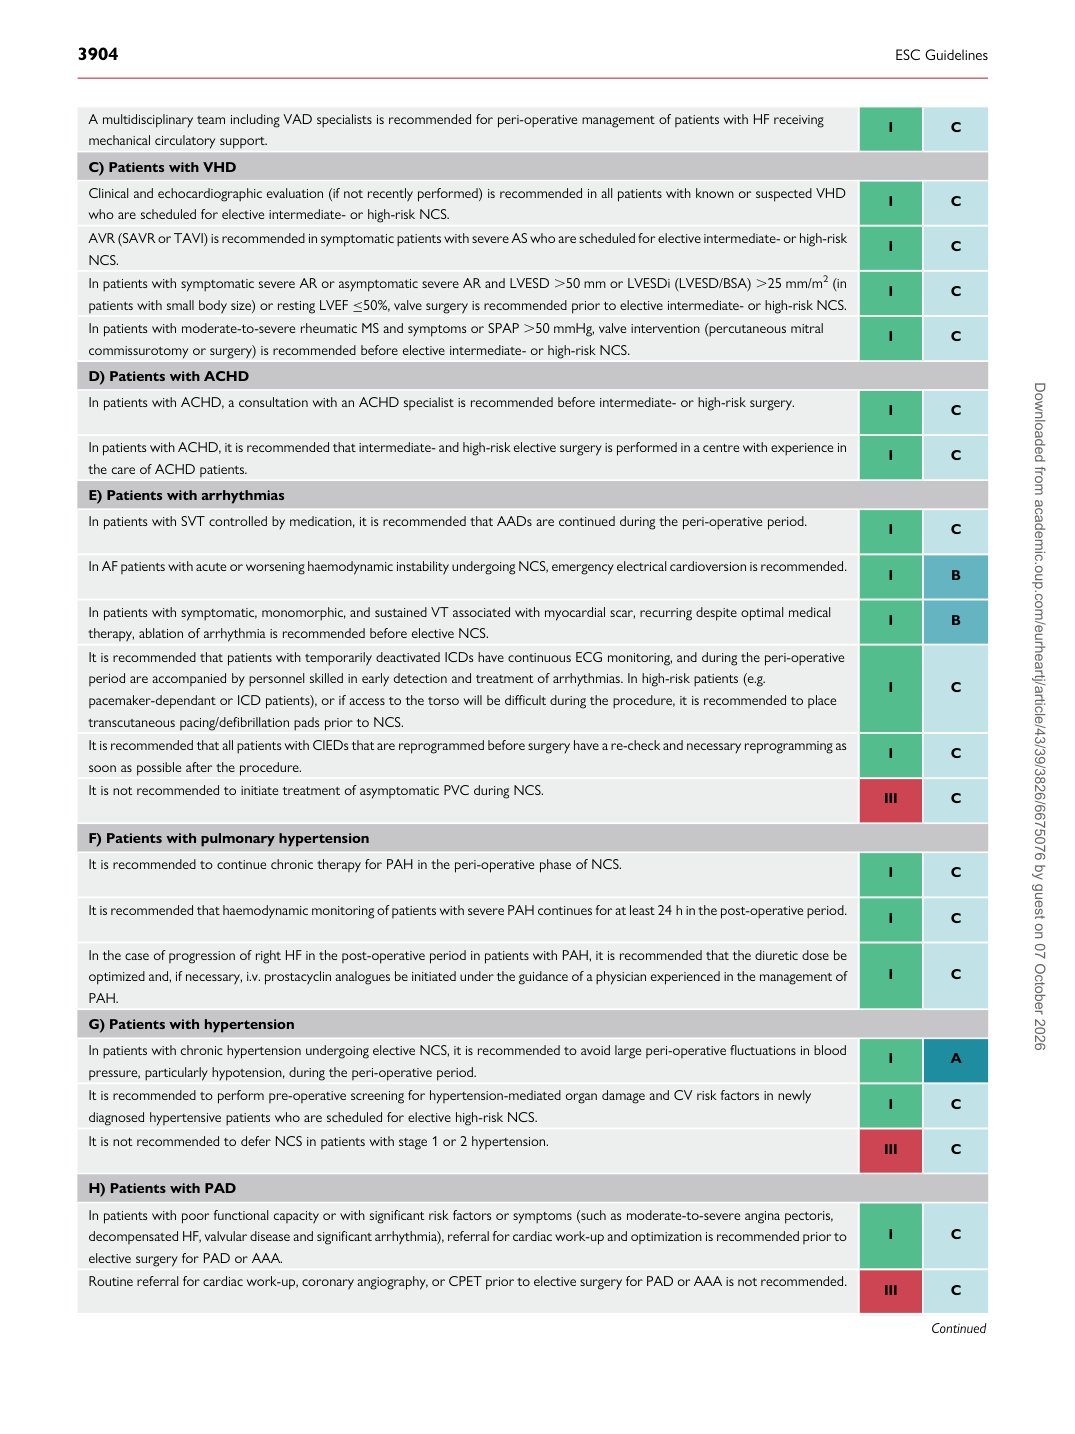
A multidisciplinary team including VAD specialists is recommended for peri-operative management of patients with HF receiving mechanical circulatory support. I C C) Patients with VHD Clinical and echocardiographic evaluation (if not recently performed) is recommended in all patients with known or suspected VHD who are scheduled for elective intermediate- or high-risk NCS. I C AVR (SAVR or TAVI) is recommended in symptomatic patients with severe AS who are scheduled for elective intermediate- or high-risk NCS. I C In patients with symptomatic severe AR or asymptomatic severe AR and LVESD .50 mm or LVESDi (LVESD/BSA) .25 mm/m2 (in patients with small body size) or resting LVEF ≤50%, valve surgery is recommended prior to elective intermediate- or high-risk NCS. I C In patients with moderate-to-severe rheumatic MS and symptoms or SPAP .50 mmHg, valve intervention (percutaneous mitral commissurotomy or surgery) is recommended before elective intermediate- or high-risk NCS. I C D) Patients with ACHD In patients with ACHD, a consultation with an ACHD specialist is recommended before intermediate- or high-risk surgery. I C

In patients with ACHD, it is recommended that intermediate- and high-risk elective surgery is performed in a centre with experience in the care of ACHD patients. I C E) Patients with arrhythmias In patients with SVT controlled by medication, it is recommended that AADs are continued during the peri-operative period. I C

In AF patients with acute or worsening haemodynamic instability undergoing NCS, emergency electrical cardioversion is recommended. I B

In patients with symptomatic, monomorphic, and sustained VT associated with myocardial scar, recurring despite optimal medical therapy, ablation of arrhythmia is recommended before elective NCS. I B It is recommended that patients with temporarily deactivated ICDs have continuous ECG monitoring, and during the peri-operative period are accompanied by personnel skilled in early detection and treatment of arrhythmias. In high-risk patients (e.g. pacemaker-dependant or ICD patients), or if access to the torso will be difficult during the procedure, it is recommended to place transcutaneous pacing/defibrillation pads prior to NCS. I C It is recommended that all patients with CIEDs that are reprogrammed before surgery have a re-check and necessary reprogramming as soon as possible after the procedure. I C It is not recommended to initiate treatment of asymptomatic PVC during NCS. III C

F) Patients with pulmonary hypertension It is recommended to continue chronic therapy for PAH in the peri-operative phase of NCS. I C

It is recommended that haemodynamic monitoring of patients with severe PAH continues for at least 24 h in the post-operative period. I C

In the case of progression of right HF in the post-operative period in patients with PAH, it is recommended that the diuretic dose be optimized and, if necessary, i.v. prostacyclin analogues be initiated under the guidance of a physician experienced in the management of PAH. I C G) Patients with hypertension In patients with chronic hypertension undergoing elective NCS, it is recommended to avoid large peri-operative fluctuations in blood pressure, particularly hypotension, during the peri-operative period. I A It is recommended to perform pre-operative screening for hypertension-mediated organ damage and CV risk factors in newly diagnosed hypertensive patients who are scheduled for elective high-risk NCS. I C It is not recommended to defer NCS in patients with stage 1 or 2 hypertension. III C

H) Patients with PAD In patients with poor functional capacity or with significant risk factors or symptoms (such as moderate-to-severe angina pectoris, decompensated HF, valvular disease and significant arrhythmia), referral for cardiac work-up and optimization is recommended prior to elective surgery for PAD or AAA. I C Routine referral for cardiac work-up, coronary angiography, or CPET prior to elective surgery for PAD or AAA is not recommended. III C

Continued Downloaded from academic.oup.com/eurheartj/article/43/39/3826/6675076 by guest on 07 October 2026