p.42 抽出テキスト
The use of amiodarone, verapamil, or diltiazem was also associated with elevated pre-operative NOAC levels in the prospective Per-procedural Concentration of Direct Oral Anticoagulants (CORIDA) trial.310 Importantly, elevated NOAC levels were not found to be independently associated with bleeding complications.309,310 The evidence base for modifying the duration of pre-operative NOAC interruption time intervals according to residual NOAC plasma levels is unavailable, and ‘safe’ plasma levels of NOACs for different procedures are largely unknown. The time-based NOAC interruption (Figure 9) appears safe in most patients undergoing surgery.311,312 When NOACs are interrupted for .72 h, the likelihood of any residual NOAC plasma levels is very low.309,310 5.3.2.2.5 Considerations for specific procedures. Before interven-

tions that carry a very high risk of bleeding—such as spinal or epidural anaesthesia, or lumbar puncture requiring intact haemostasis-–interruption of NOACs for up to five half-lives (i.e. 3 days for FXa inhibitors or 4–5 days for dabigatran) should be considered, whereas NOACs can usually be restarted 24 h after the intervention.313,314 Dental procedures are generally considered to be associated with minor bleeding risk, and adequate local haemostasis is usually easily achieved. Hence, most dental procedures can be performed in an outpatient setting, with uninterrupted NOAC (or a single skipped dose) and using specific local haemostatic measures (such as the application of oxidized cellulose or absorbable gelatine sponge, sutures,

Strate g y f or potential

f f r e v ersal of non-vitamin K oral anticoagulants ef f f f ect

f f

P er f orm NCS

f f

P er f orm NCS

f f

T argeted haemostatic measu

T

T r es

P er f orm NCS

f f

N N N Y Y Y

Deg r ee of urgency

Last inta k e of N

N

k k O A Cs >12 h c

Check f or blood coagulation tests:

f f

full coagulation panel (P T ,

T

T aPT

, T ,

T

T antiFXa

, , dT

, T ,

T

T et

, c .)

Measu r ement of N OA C plasma l e v els , if

, a vailable

a a

Recheck coagulation panel if last N O A C inta k e <12 h,

k k c

or initial coagulation tests pathological, or clinical l y r el e vant bleeding situation

Surge r y de f e

f f r ral f or 12 h,

f f c

if sa f e

f f , or after normalization

, of coagulation parameters e

R e v ersal of N O A C depending on:

Surge r y de f e

f f r ral as f or planned

f f

p r ocedu r es , if sa

, f e (see Figu

f f r e 8)

Surge r y- r elated bleeding risk and agent a vailability

a a d

IMMEDI A TE

A

A i. e . within mi

. n utes URGENT

i. e . within hours

. a TIME-SENSITIVE

i. e . within d

. a ys

a a b

Step 1 Urgr ency

Step 2 Blood coagulation

Step 3 Timing last NOA O C

Step 4 NCS

Step 5 Recheck blood coagulation

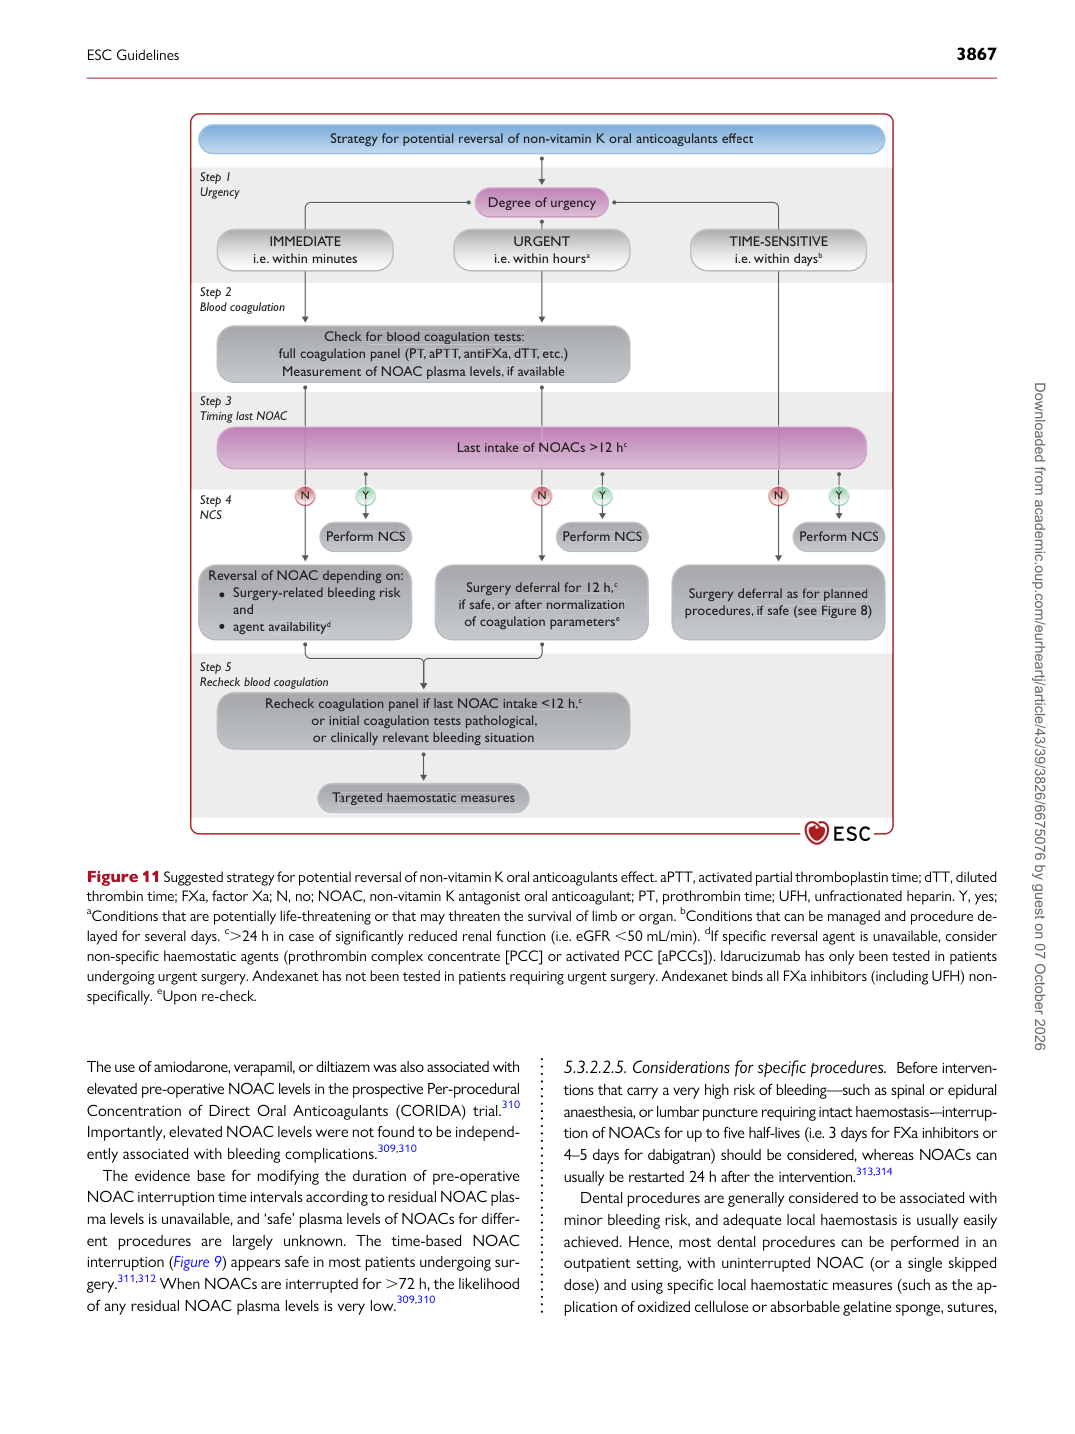
Figure 11 Suggested strategy for potential reversal of non-vitamin K oral anticoagulants effect. aPTT, activated partial thromboplastin time; dTT, diluted thrombin time; FXa, factor Xa; N, no; NOAC, non-vitamin K antagonist oral anticoagulant; PT, prothrombin time; UFH, unfractionated heparin. Y, yes; aConditions that are potentially life-threatening or that may threaten the survival of limb or organ. bConditions that can be managed and procedure delayed for several days. c.24 h in case of significantly reduced renal function (i.e. eGFR ,50 mL/min). dIf specific reversal agent is unavailable, consider non-specific haemostatic agents (prothrombin complex concentrate [PCC] or activated PCC [aPCCs]). Idarucizumab has only been tested in patients undergoing urgent surgery. Andexanet has not been tested in patients requiring urgent surgery. Andexanet binds all FXa inhibitors (including UFH) nonspecifically. eUpon re-check.

ESC Guidelines                                                                                                                                                                                     3867

Downloaded from academic.oup.com/eurheartj/article/43/39/3826/6675076 by guest on 07 October 2026