p.34 抽出テキスト
The trial randomized 10 010 patients undergoing NCS with established CVD, or who were at increased CV risk, to aspirin or placebo. Patients were stratified according to whether they had not been taking aspirin before the study or were already on aspirin; 33% of the patients had known vascular disease (23% CAD, 9% PAD, and 5% stroke). Aspirin did not reduce the rates of death or non-fatal MI at 30 days (7.0% vs. 7.1% in the placebo group [HR, 0.99; 95% CI, 0.86–1.15; P = 0.92]). Major bleeding was more common in the aspirin group than in the placebo group (4.6% vs. 3.8% [HR, 1.23; 95% CI, 1.01–1.49; P = 0.04]). The primary outcome results were similar, irrespective of whether or not patients had been taking aspirin before the study, and were also similar in patients with and without vascular disease. In a post hoc analysis of 470 patients (,5%) who had undergone previous PCI, aspirin use was associated with a significant reduction in death or MI (HR, 0.50; 95% CI, 0.26–0.95; P = 0.036) and MI alone (HR, 0.44; 95% CI, 0.22–0.87; P = 0.021), while the risk of major or life-threatening bleeding was not significantly increased in this setting.244 Although the analysis carries several limitations, it supports the perception that the ischaemic benefit of peri-operative aspirin use outweighs the bleeding risk in patients with previous PCI. Thus, among patients with previous PCI, in the absence of a very high bleeding risk, low-dose aspirin should be continued during the peri-operative period.

In patients undergoing transcatheter aortic valve implantation (TAVI) who have no other indication for oral anticoagulant (OAC) therapy, low-dose aspirin has been recommended as standard therapy by recent guidelines based on an RCT.245,246 There are no randomized data available assessing the withdrawal vs. continuation of aspirin in patients after TAVI on aspirin alone undergoing NCS. If the bleeding risk outweighs the potential CV benefit, aspirin should be discontinued. For patients with high peri-operative bleeding risk (e.g. undergoing spinal surgery or certain neurosurgical or ophthalmological operations) aspirin should be discontinued for at least 7 days. On rare occasions, chronic coronary syndrome (CCS) patients might be on clopidogrel monotherapy due to the results of recent trials247 and the recommendations of the 2020 ESC Guidelines for

NCS-related bleeding risk

N

N

N Patients on dual antiplatelet ther a p y

p

Y

Y

Y

High bleeding risk r elated to NCS

High th r ombotic risk:

PCI <1 month or A CS <3 months or High risk of stent th r ombosis a

Conti n ue aspirin

(Class I) De f er NCS

f f (Class I)

Time-sensiti v e NCS

Thrombotic risk

Recommendations

Conti n ue D APT

D

D

Ticag r elo r : 3–5 d

: a ys

a a

Clopidog r el : 5 d

: a ys

a a

Prasug r el : 7 d

: a ys

a a (Class I) Bridge with GPI

or cang r elor c

Inte r rupt P2Y

12 inhibitor

b (Class IIa/b)

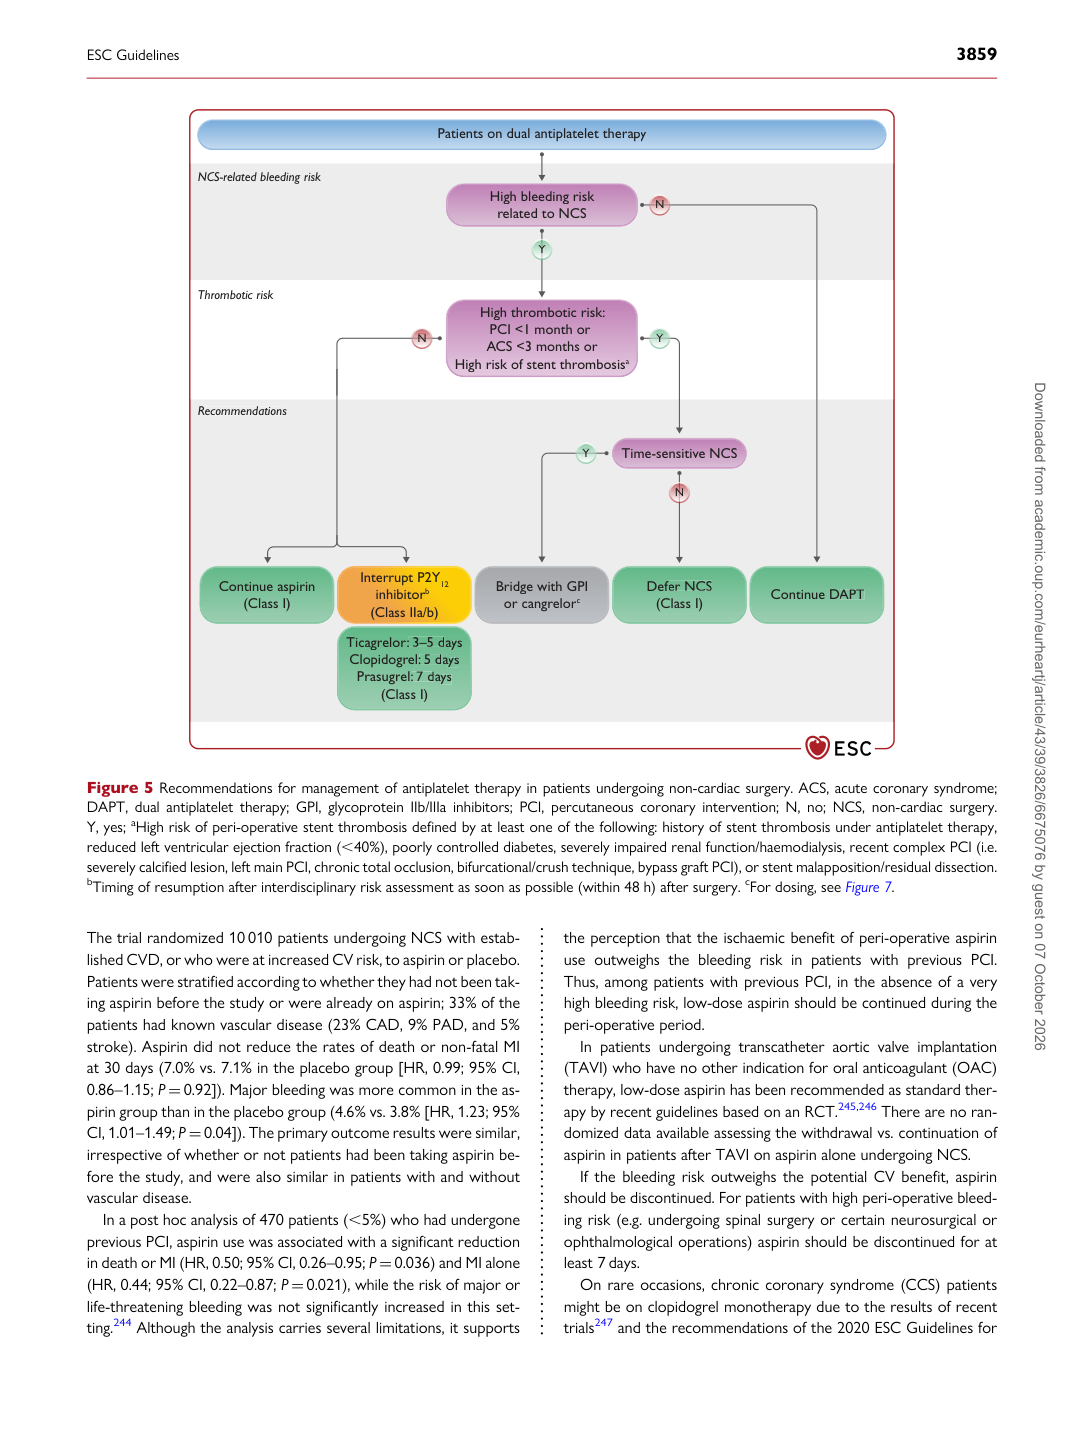
Figure 5 Recommendations for management of antiplatelet therapy in patients undergoing non-cardiac surgery. ACS, acute coronary syndrome; DAPT, dual antiplatelet therapy; GPI, glycoprotein IIb/IIIa inhibitors; PCI, percutaneous coronary intervention; N, no; NCS, non-cardiac surgery. Y, yes; aHigh risk of peri-operative stent thrombosis defined by at least one of the following: history of stent thrombosis under antiplatelet therapy, reduced left ventricular ejection fraction (,40%), poorly controlled diabetes, severely impaired renal function/haemodialysis, recent complex PCI (i.e. severely calcified lesion, left main PCI, chronic total occlusion, bifurcational/crush technique, bypass graft PCI), or stent malapposition/residual dissection. bTiming of resumption after interdisciplinary risk assessment as soon as possible (within 48 h) after surgery. cFor dosing, see Figure 7.

ESC Guidelines                                                                                                                                                                                     3859

Downloaded from academic.oup.com/eurheartj/article/43/39/3826/6675076 by guest on 07 October 2026