p.57 抽出テキスト
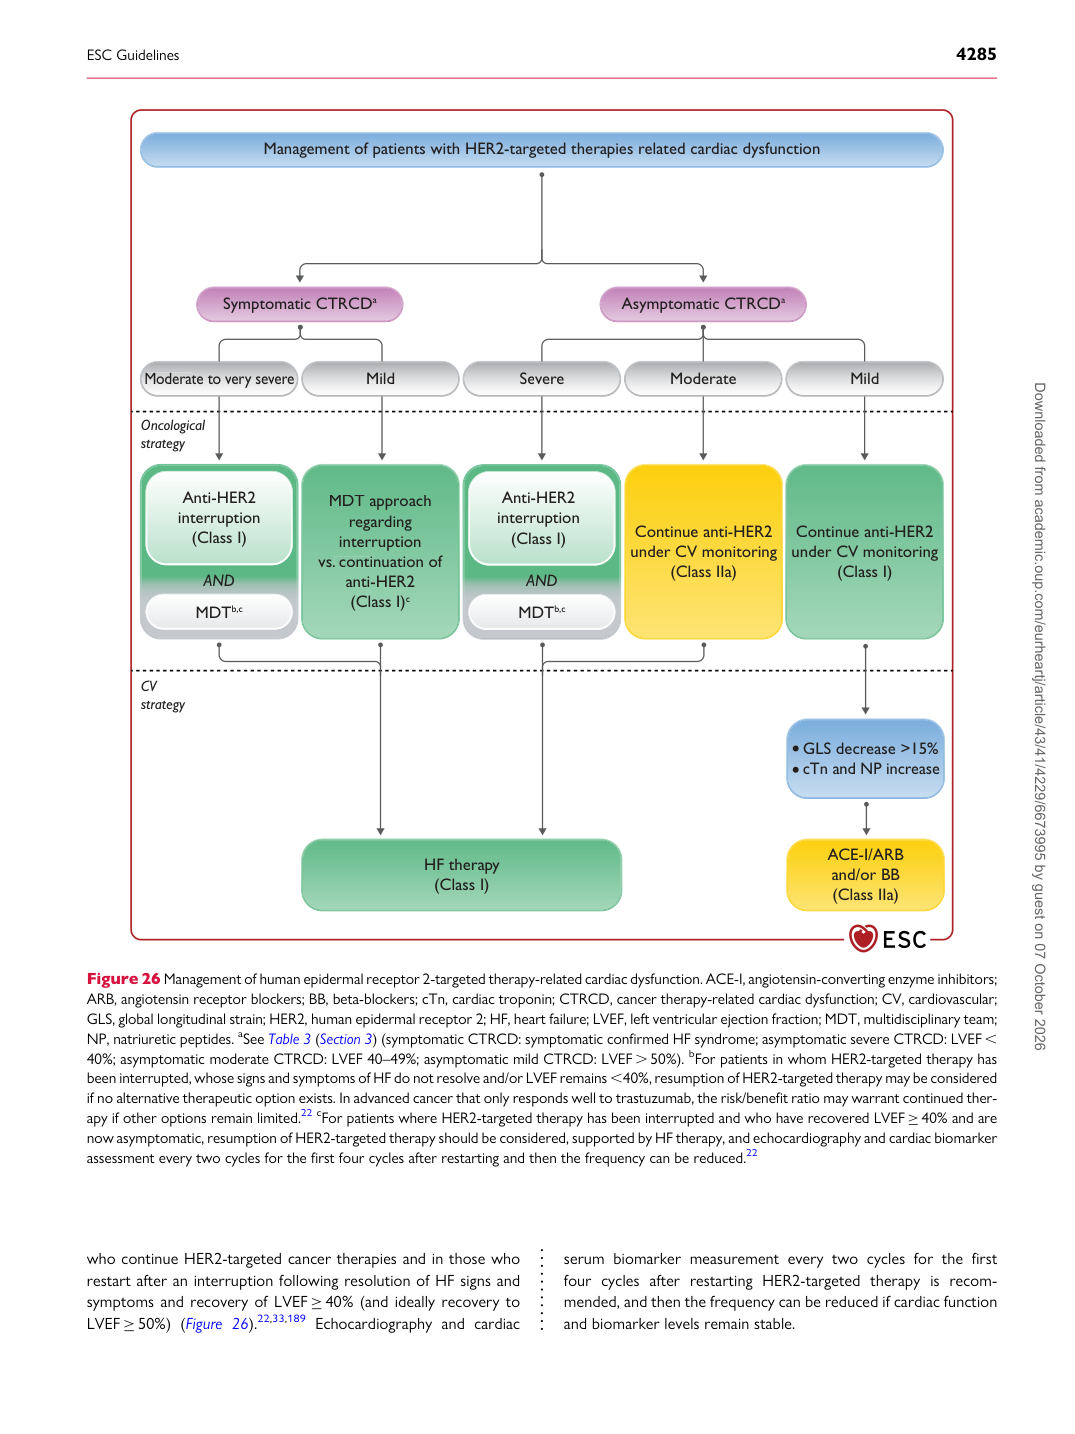
who continue HER2-targeted cancer therapies and in those who restart after an interruption following resolution of HF signs and symptoms and recovery of LVEF ≥40% (and ideally recovery to LVEF ≥50%) (Figure 26).22,33,189 Echocardiography and cardiac serum biomarker measurement every two cycles for the first four cycles after restarting HER2-targeted therapy is recommended, and then the frequency can be reduced if cardiac function and biomarker levels remain stable.

Anti-HER2 inte r ruption

(Class I) Anti-HER2

inte r ruption

(Class I)

MDT a pp r oach

r ega r ding inte r ruption vs . conti

. n uation of

anti-HER2 (Class I) c Conti n ue anti-HER2

under CV monitoring

(Class I)

Conti n ue anti-HER2 under CV monitoring

(Class IIa)

Symptomatic CTRCD a

Modera t

a a e t o v e r y s e v e r e

Oncological strategy

CV strategy Mild

MDT b ,c S e v e r e Moderate Mild

A CE-I/ARB and/or BB (Class IIa)

HF ther a p y

p p (Class I) Asymptomatic CTRCD a

Management of patients with HER2-targeted ther a pies r elated ca r diac dysfunction

AND

MDT b ,c

AND

GLS dec r ease >15% cT n a n d NP i nc r eas e

Figure 26 Management of human epidermal receptor 2-targeted therapy-related cardiac dysfunction. ACE-I, angiotensin-converting enzyme inhibitors; ARB, angiotensin receptor blockers; BB, beta-blockers; cTn, cardiac troponin; CTRCD, cancer therapy-related cardiac dysfunction; CV, cardiovascular; GLS, global longitudinal strain; HER2, human epidermal receptor 2; HF, heart failure; LVEF, left ventricular ejection fraction; MDT, multidisciplinary team; NP, natriuretic peptides. aSee Table 3 (Section 3) (symptomatic CTRCD: symptomatic confirmed HF syndrome; asymptomatic severe CTRCD: LVEF , 40%; asymptomatic moderate CTRCD: LVEF 40–49%; asymptomatic mild CTRCD: LVEF . 50%). bFor patients in whom HER2-targeted therapy has been interrupted, whose signs and symptoms of HF do not resolve and/or LVEF remains ,40%, resumption of HER2-targeted therapy may be considered if no alternative therapeutic option exists. In advanced cancer that only responds well to trastuzumab, the risk/benefit ratio may warrant continued therapy if other options remain limited.22 cFor patients where HER2-targeted therapy has been interrupted and who have recovered LVEF ≥40% and are now asymptomatic, resumption of HER2-targeted therapy should be considered, supported by HF therapy, and echocardiography and cardiac biomarker assessment every two cycles for the first four cycles after restarting and then the frequency can be reduced.22 Downloaded from academic.oup.com/eurheartj/article/43/41/4229/6673995 by guest on 07 October 2026