p.109 抽出テキスト
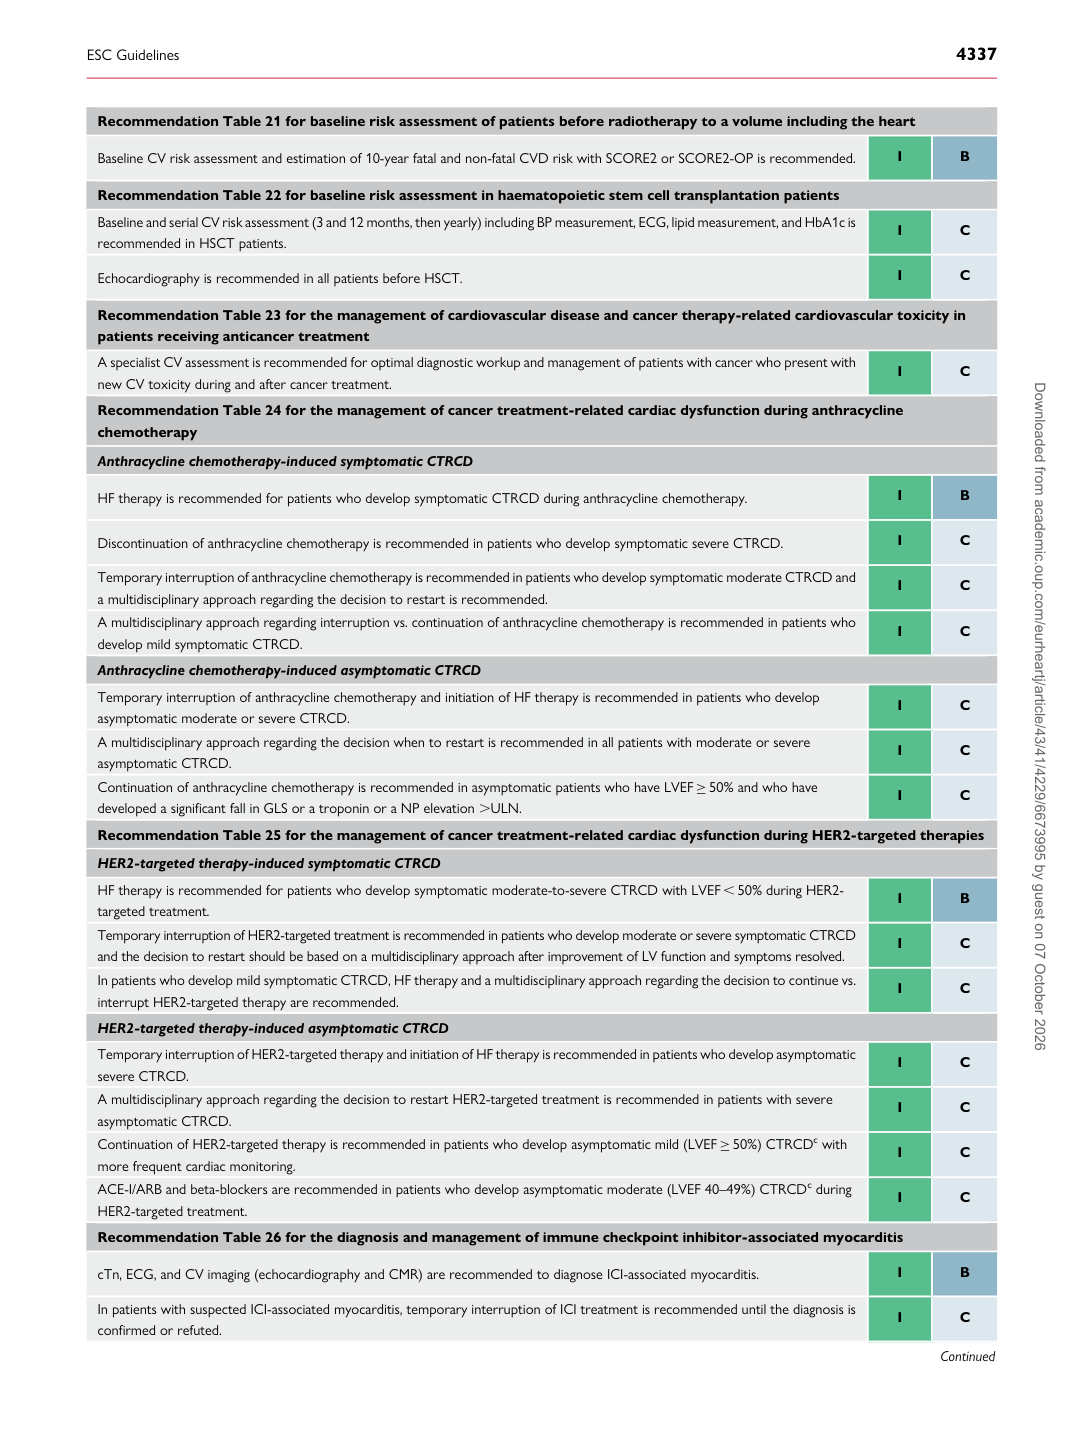
Recommendation Table 21 for baseline risk assessment of patients before radiotherapy to a volume including the heart

Baseline CV risk assessment and estimation of 10-year fatal and non-fatal CVD risk with SCORE2 or SCORE2-OP is recommended. I B

Recommendation Table 22 for baseline risk assessment in haematopoietic stem cell transplantation patients Baseline and serial CV risk assessment (3 and 12 months, then yearly) including BP measurement, ECG, lipid measurement, and HbA1c is recommended in HSCT patients. I C

Echocardiography is recommended in all patients before HSCT. I C

Recommendation Table 23 for the management of cardiovascular disease and cancer therapy-related cardiovascular toxicity in patients receiving anticancer treatment A specialist CV assessment is recommended for optimal diagnostic workup and management of patients with cancer who present with new CV toxicity during and after cancer treatment. I C Recommendation Table 24 for the management of cancer treatment-related cardiac dysfunction during anthracycline chemotherapy Anthracycline chemotherapy-induced symptomatic CTRCD

HF therapy is recommended for patients who develop symptomatic CTRCD during anthracycline chemotherapy. I B

Discontinuation of anthracycline chemotherapy is recommended in patients who develop symptomatic severe CTRCD. I C

Temporary interruption of anthracycline chemotherapy is recommended in patients who develop symptomatic moderate CTRCD and a multidisciplinary approach regarding the decision to restart is recommended. I C A multidisciplinary approach regarding interruption vs. continuation of anthracycline chemotherapy is recommended in patients who develop mild symptomatic CTRCD. I C Anthracycline chemotherapy-induced asymptomatic CTRCD Temporary interruption of anthracycline chemotherapy and initiation of HF therapy is recommended in patients who develop asymptomatic moderate or severe CTRCD. I C A multidisciplinary approach regarding the decision when to restart is recommended in all patients with moderate or severe asymptomatic CTRCD. I C Continuation of anthracycline chemotherapy is recommended in asymptomatic patients who have LVEF ≥50% and who have developed a significant fall in GLS or a troponin or a NP elevation .ULN. I C Recommendation Table 25 for the management of cancer treatment-related cardiac dysfunction during HER2-targeted therapies HER2-targeted therapy-induced symptomatic CTRCD HF therapy is recommended for patients who develop symptomatic moderate-to-severe CTRCD with LVEF , 50% during HER2targeted treatment. I B Temporary interruption of HER2-targeted treatment is recommended in patients who develop moderate or severe symptomatic CTRCD and the decision to restart should be based on a multidisciplinary approach after improvement of LV function and symptoms resolved. I C In patients who develop mild symptomatic CTRCD, HF therapy and a multidisciplinary approach regarding the decision to continue vs. interrupt HER2-targeted therapy are recommended. I C HER2-targeted therapy-induced asymptomatic CTRCD Temporary interruption of HER2-targeted therapy and initiation of HF therapy is recommended in patients who develop asymptomatic severe CTRCD. I C A multidisciplinary approach regarding the decision to restart HER2-targeted treatment is recommended in patients with severe asymptomatic CTRCD. I C Continuation of HER2-targeted therapy is recommended in patients who develop asymptomatic mild (LVEF ≥50%) CTRCDc with more frequent cardiac monitoring. I C ACE-I/ARB and beta-blockers are recommended in patients who develop asymptomatic moderate (LVEF 40–49%) CTRCDc during HER2-targeted treatment. I C Recommendation Table 26 for the diagnosis and management of immune checkpoint inhibitor-associated myocarditis

cTn, ECG, and CV imaging (echocardiography and CMR) are recommended to diagnose ICI-associated myocarditis. I B

In patients with suspected ICI-associated myocarditis, temporary interruption of ICI treatment is recommended until the diagnosis is confirmed or refuted. I C

Continued Downloaded from academic.oup.com/eurheartj/article/43/41/4229/6673995 by guest on 07 October 2026