p.11 抽出テキスト
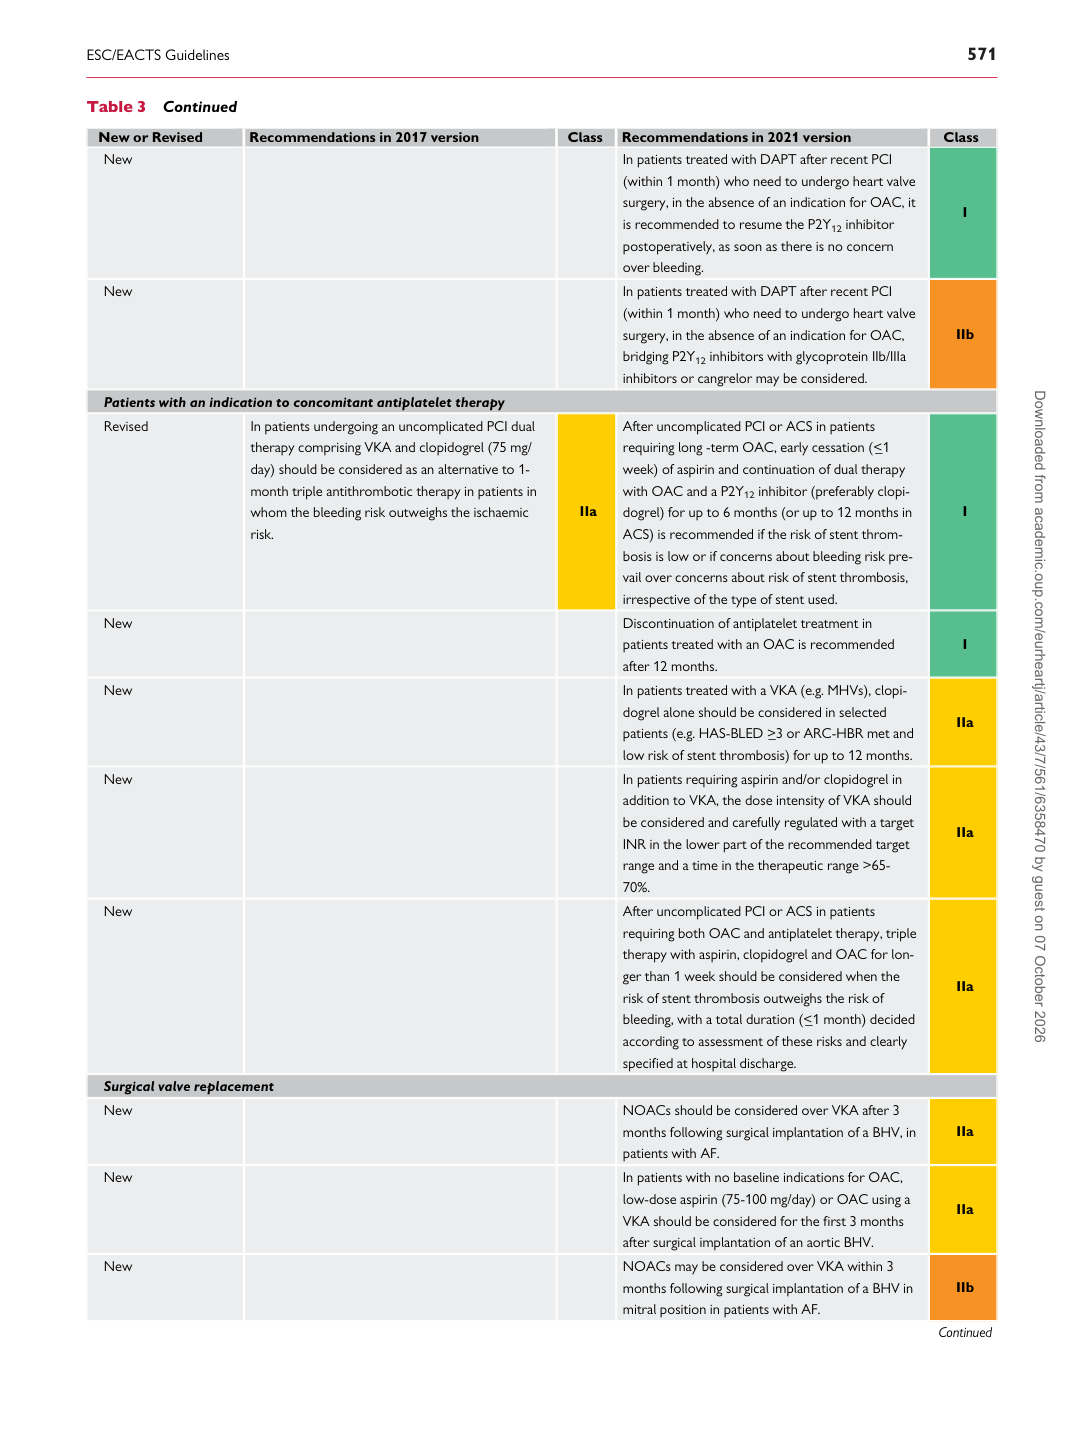
Table 3 Continued

New or Revised Recommendations in 2017 version Class Recommendations in 2021 version Class New In patients treated with DAPT after recent PCI (within 1 month) who need to undergo heart valve

surgery, in the absence of an indication for OAC, it is recommended to resume the P2Y12 inhibitor postoperatively, as soon as there is no concern over bleeding. I

New In patients treated with DAPT after recent PCI (within 1 month) who need to undergo heart valve

surgery, in the absence of an indication for OAC, bridging P2Y12 inhibitors with glycoprotein IIb/IIIa inhibitors or cangrelor may be considered. IIb

Patients with an indication to concomitant antiplatelet therapy Revised In patients undergoing an uncomplicated PCI dual

therapy comprising VKA and clopidogrel (75 mg/ day) should be considered as an alternative to 1month triple antithrombotic therapy in patients in whom the bleeding risk outweighs the ischaemic risk. IIa After uncomplicated PCI or ACS in patients

requiring long -term OAC, early cessation (<_1 week) of aspirin and continuation of dual therapy with OAC and a P2Y12 inhibitor (preferably clopidogrel) for up to 6 months (or up to 12 months in ACS) is recommended if the risk of stent thrombosis is low or if concerns about bleeding risk prevail over concerns about risk of stent thrombosis, irrespective of the type of stent used. I

New Discontinuation of antiplatelet treatment in

patients treated with an OAC is recommended after 12 months. I

New In patients treated with a VKA (e.g. MHVs), clopi-

dogrel alone should be considered in selected patients (e.g. HAS-BLED >_3 or ARC-HBR met and low risk of stent thrombosis) for up to 12 months. IIa

New In patients requiring aspirin and/or clopidogrel in

addition to VKA, the dose intensity of VKA should be considered and carefully regulated with a target INR in the lower part of the recommended target range and a time in the therapeutic range >65- 70%. IIa

New After uncomplicated PCI or ACS in patients

requiring both OAC and antiplatelet therapy, triple therapy with aspirin, clopidogrel and OAC for longer than 1 week should be considered when the risk of stent thrombosis outweighs the risk of bleeding, with a total duration (<_1 month) decided according to assessment of these risks and clearly specified at hospital discharge. IIa

Surgical valve replacement New NOACs should be considered over VKA after 3 months following surgical implantation of a BHV, in

patients with AF. IIa

New In patients with no baseline indications for OAC,

low-dose aspirin (75-100 mg/day) or OAC using a VKA should be considered for the first 3 months after surgical implantation of an aortic BHV. IIa

New NOACs may be considered over VKA within 3 months following surgical implantation of a BHV in

mitral position in patients with AF. IIb

Continued Downloaded from academic.oup.com/eurheartj/article/43/7/561/6358470 by guest on 07 October 2026