p.13 抽出テキスト
Table 3 Continued

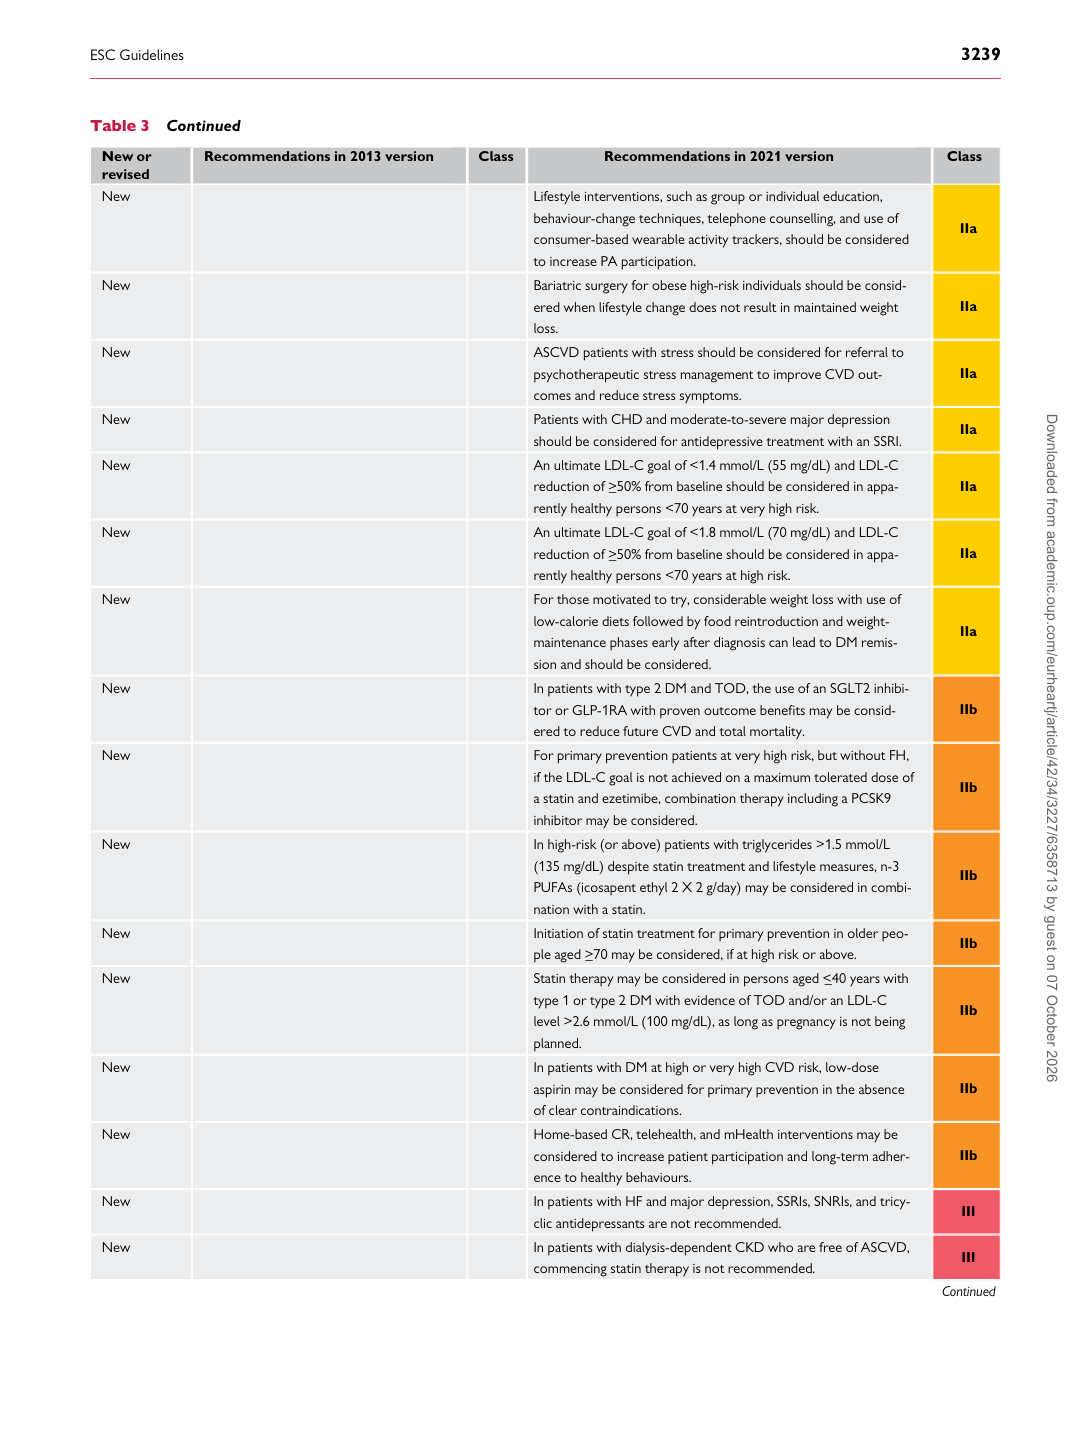
New or revised Recommendations in 2013 version Class Recommendations in 2021 version Class New Lifestyle interventions, such as group or individual education,

behaviour-change techniques, telephone counselling, and use of consumer-based wearable activity trackers, should be considered to increase PA participation. IIa

New Bariatric surgery for obese high-risk individuals should be consid-

ered when lifestyle change does not result in maintained weight loss. IIa

New ASCVD patients with stress should be considered for referral to

psychotherapeutic stress management to improve CVD outcomes and reduce stress symptoms. IIa

New Patients with CHD and moderate-to-severe major depression should be considered for antidepressive treatment with an SSRI. IIa New An ultimate LDL-C goal of <1.4 mmol/L (55 mg/dL) and LDL-C

reduction of >_50% from baseline should be considered in apparently healthy persons <70 years at very high risk. IIa

New An ultimate LDL-C goal of <1.8 mmol/L (70 mg/dL) and LDL-C

reduction of >_50% from baseline should be considered in apparently healthy persons <70 years at high risk. IIa

New For those motivated to try, considerable weight loss with use of

low-calorie diets followed by food reintroduction and weightmaintenance phases early after diagnosis can lead to DM remission and should be considered. IIa

New In patients with type 2 DM and TOD, the use of an SGLT2 inhibi-

tor or GLP-1RA with proven outcome benefits may be considered to reduce future CVD and total mortality. IIb

New For primary prevention patients at very high risk, but without FH,

if the LDL-C goal is not achieved on a maximum tolerated dose of a statin and ezetimibe, combination therapy including a PCSK9 inhibitor may be considered. IIb

New In high-risk (or above) patients with triglycerides >1.5 mmol/L

(135 mg/dL) despite statin treatment and lifestyle measures, n-3 PUFAs (icosapent ethyl 2 X 2 g/day) may be considered in combination with a statin. IIb

New Initiation of statin treatment for primary prevention in older peo-

ple aged >_70 may be considered, if at high risk or above. IIb

New Statin therapy may be considered in persons aged <_40 years with type 1 or type 2 DM with evidence of TOD and/or an LDL-C

level >2.6 mmol/L (100 mg/dL), as long as pregnancy is not being planned. IIb

New In patients with DM at high or very high CVD risk, low-dose

aspirin may be considered for primary prevention in the absence of clear contraindications. IIb

New Home-based CR, telehealth, and mHealth interventions may be

considered to increase patient participation and long-term adherence to healthy behaviours. IIb

New In patients with HF and major depression, SSRIs, SNRIs, and tricyclic antidepressants are not recommended. III New In patients with dialysis-dependent CKD who are free of ASCVD,

commencing statin therapy is not recommended. III

Continued Downloaded from academic.oup.com/eurheartj/article/42/34/3227/6358713 by guest on 07 October 2026