p.78 抽出テキスト
................ existing, but previously undiagnosed, causes of HF such as CMPs and valve diseases.885 Symptoms are more likely to occur in the second trimester when the demand for an increased cardiac output is the highest. Severe emotionally stressful episodes during pregnancy and delivery can also cause Takotsubo syndrome.884,885 PPCM presents as HF secondary to LV systolic dysfunction, usually shown by an LVEF <45%, occurring towards the end of pregnancy (third trimester) or in the months following delivery without any other identifiable cause. The majority of PPCM cases are diagnosed in post-partum. The prevalence ranges from 1:100 in Nigeria to 1:1000

Management of patients with heart failure before and during pregnancy

Bi-monthly or monthly review

(mWHO II) Counselling including risk assessment and educationa

Cardiac assessment including clinical assessment, ECG, echocardiogram

Review HF therapy and switch to non-teratogenic HF medication

Moderate and high-risk HF patients (mWHO II, II–III and IV)

Referral  to a specialist centre for high-risk pregnancies with multidisciplinary Pregnancy Heart Team

Reassessment at the beginning of the second trimester i.e. 20 weeks

Reassessment at 20 weeks Low-risk HF patients

(mWHO I)

Discuss with a specialist centre

for high-risk pregnancies

Reassessment at the beginning of the second trimester i.e. 20 weeks

Monthly review (mWHO III)

Urgent counselling for consideration

of pregnancy termination

(mWHO IV)

Pre-pregnancy

At pregnancy diagnosis or planning

During pregnancy

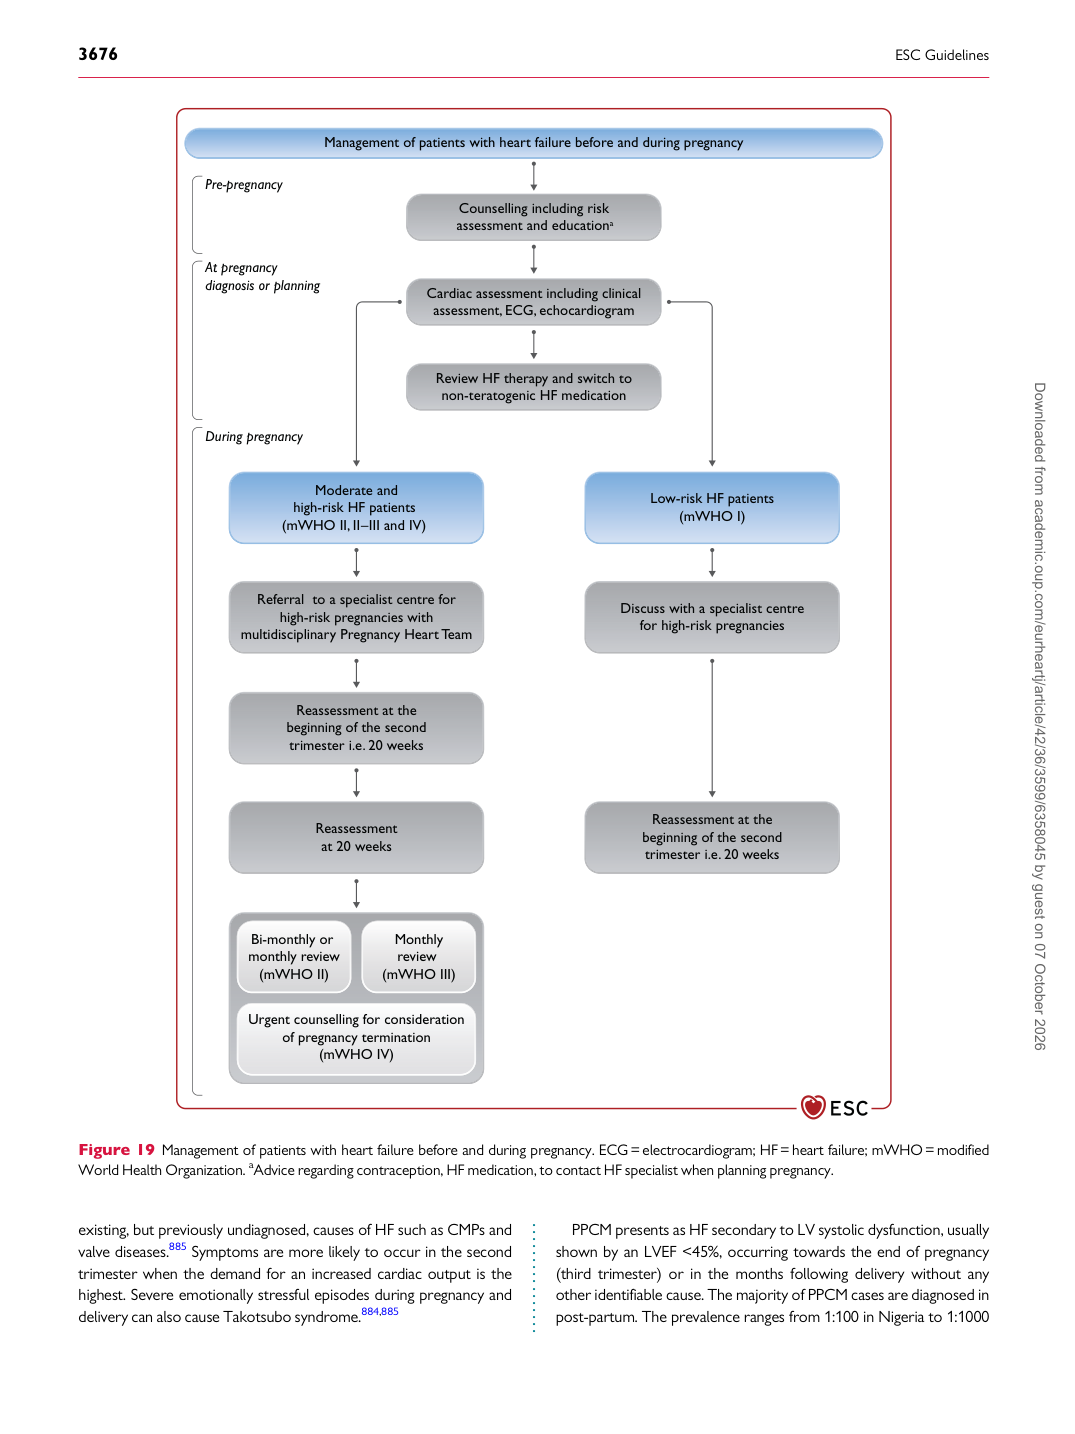
Figure 19 Management of patients with heart failure before and during pregnancy. ECG= electrocardiogram; HF= heart failure; mWHO= modified World Health Organization. aAdvice regarding contraception, HF medication, to contact HF specialist when planning pregnancy. Downloaded from academic.oup.com/eurheartj/article/42/36/3599/6358045 by guest on 07 October 2026