p.8 抽出テキスト
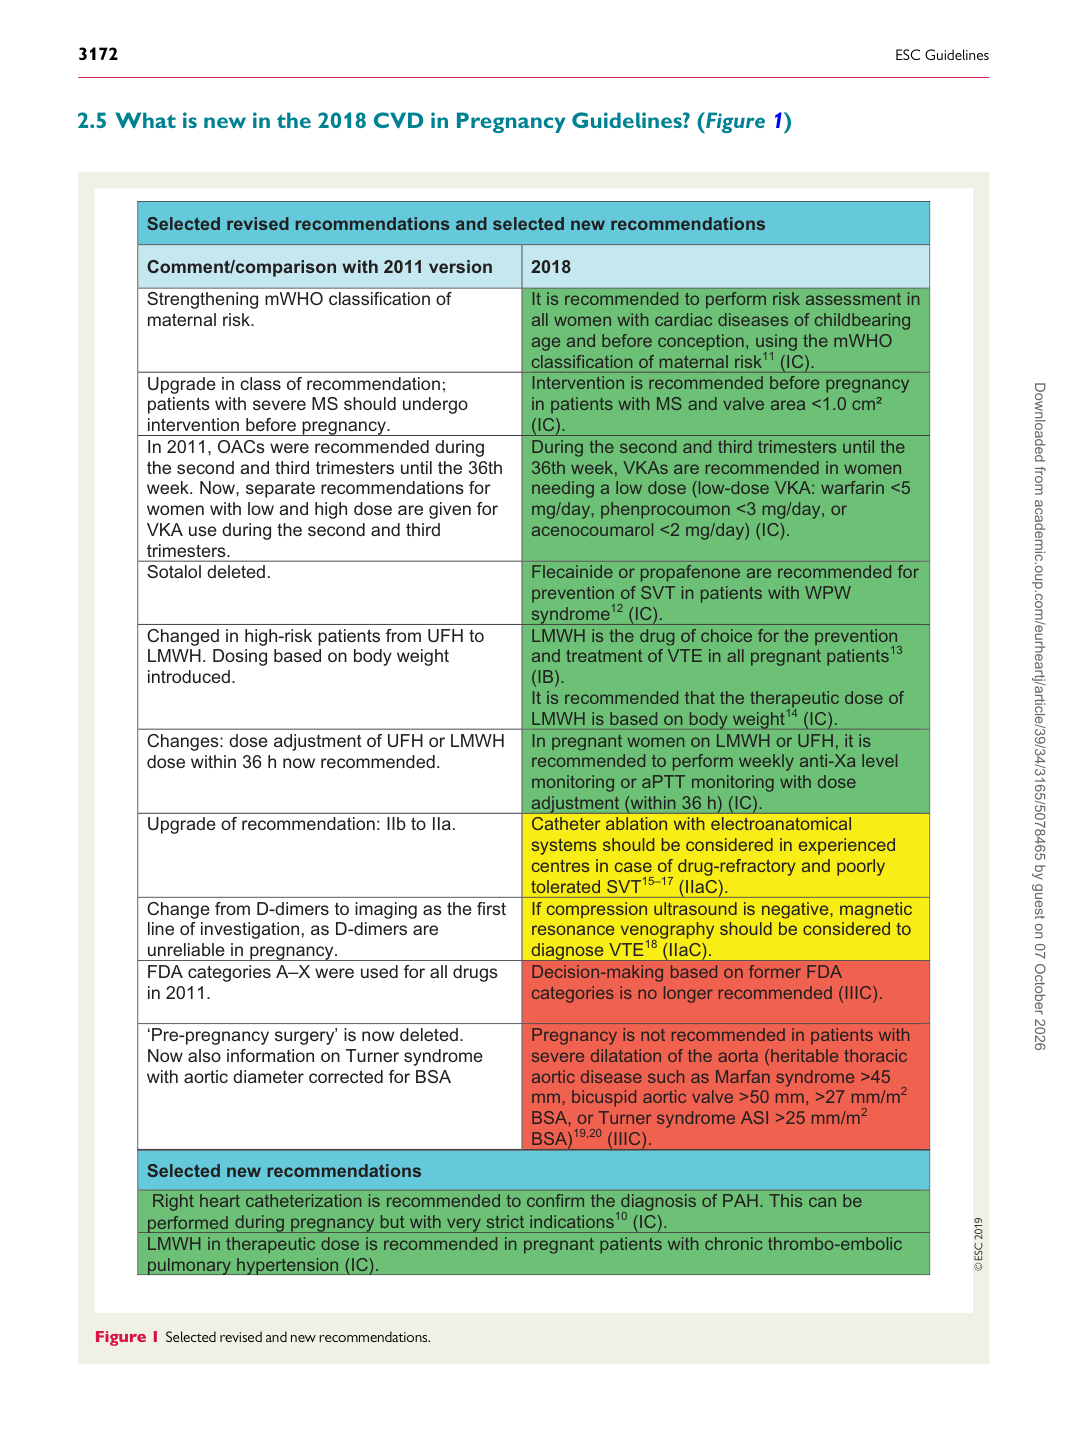
Selected new recommendations

during pregnancy but with very strict indications10 (IC). LMWH in therapeutic dose is recommended in pregnant patients with chronic thrombo-embolic pulmonary hypertension (IC).

Selected revised recommendations and selected new recommendations

Comment/comparison with 2011 version 2018 Strengthening mWHO classification of maternal risk.

It is recommended to perform risk assessment in all women with cardiac diseases of childbearing age and before conception, using the mWHO classification of maternal risk11 (IC). Upgrade in class of recommendation; patients with severe MS should undergo intervention before pregnancy.

Intervention is recommended before pregnancy in patients with MS and valve area <1.0 cm2 (IC). In 2011, OACs were recommended during the second and third trimesters until the 36th week. Now, separate recommendations for women with low and high dose are given for VKA use during the second and third trimesters.

During the second and third trimesters until the 36th week, VKAs are recommended in women needing a low dose (low-dose VKA: warfarin <5 mg/day, phenprocoumon <3 mg/day, or acenocoumarol <2 mg/day) (IC).

Sotalol deleted. Flecainide or propafenone are recommended for prevention of SVT in patients with WPW syndrome12 (IC). Changed in high-risk patients from UFH to LMWH. Dosing based on body weight introduced.

LMWH is the drug of choice for the prevention and treatment of VTE in all pregnant patients13 (IB). It is recommended that the therapeutic dose of LMWH is based on body weight14 (IC). Changes: dose adjustment of UFH or LMWH dose within 36 h now recommended.

In pregnant women on LMWH or UFH, it is recommended to perform weekly anti-Xa level monitoring or aPTT monitoring with dose adjustment (within 36 h) (IC). Upgrade of recommendation: IIb to IIa. Catheter ablation with electroanatomical systems should be considered in experienced centres in case of drug-refractory and poorly tolerated SVT15–17 (IIaC). Change from D-dimers to imaging as the first line of investigation, as D-dimers are unreliable in pregnancy.

If compression ultrasound is negative, magnetic resonance venography should be considered to diagnose VTE18 (IIaC). FDA categories A–X were used for all drugs in 2011.

‘Pre-pregnancy surgery’ is now deleted. Now also information on Turner syndrome with aortic diameter corrected for BSA Pregnancy is not recommended in patients with severe dilatation of the aorta (heritable thoracic aortic disease such as Marfan syndrome >45 mm, bicuspid aortic valve >50 mm, >27 mm/m2 BSA, or Turner syndrome ASI >25 mm/m2 BSA)19,20 (IIIC).

Decision-making based on former FDA categories is no longer recommended (IIIC).

Right heart catheterization is recommended to confirm the diagnosis of PAH. This can be performed

Figure 1 Selected revised and new recommendations.

2.5 What is new in the 2018 CVD in Pregnancy Guidelines? (Figure 1)

Downloaded from academic.oup.com/eurheartj/article/39/34/3165/5078465 by guest on 07 October 2026