p.71 抽出テキスト
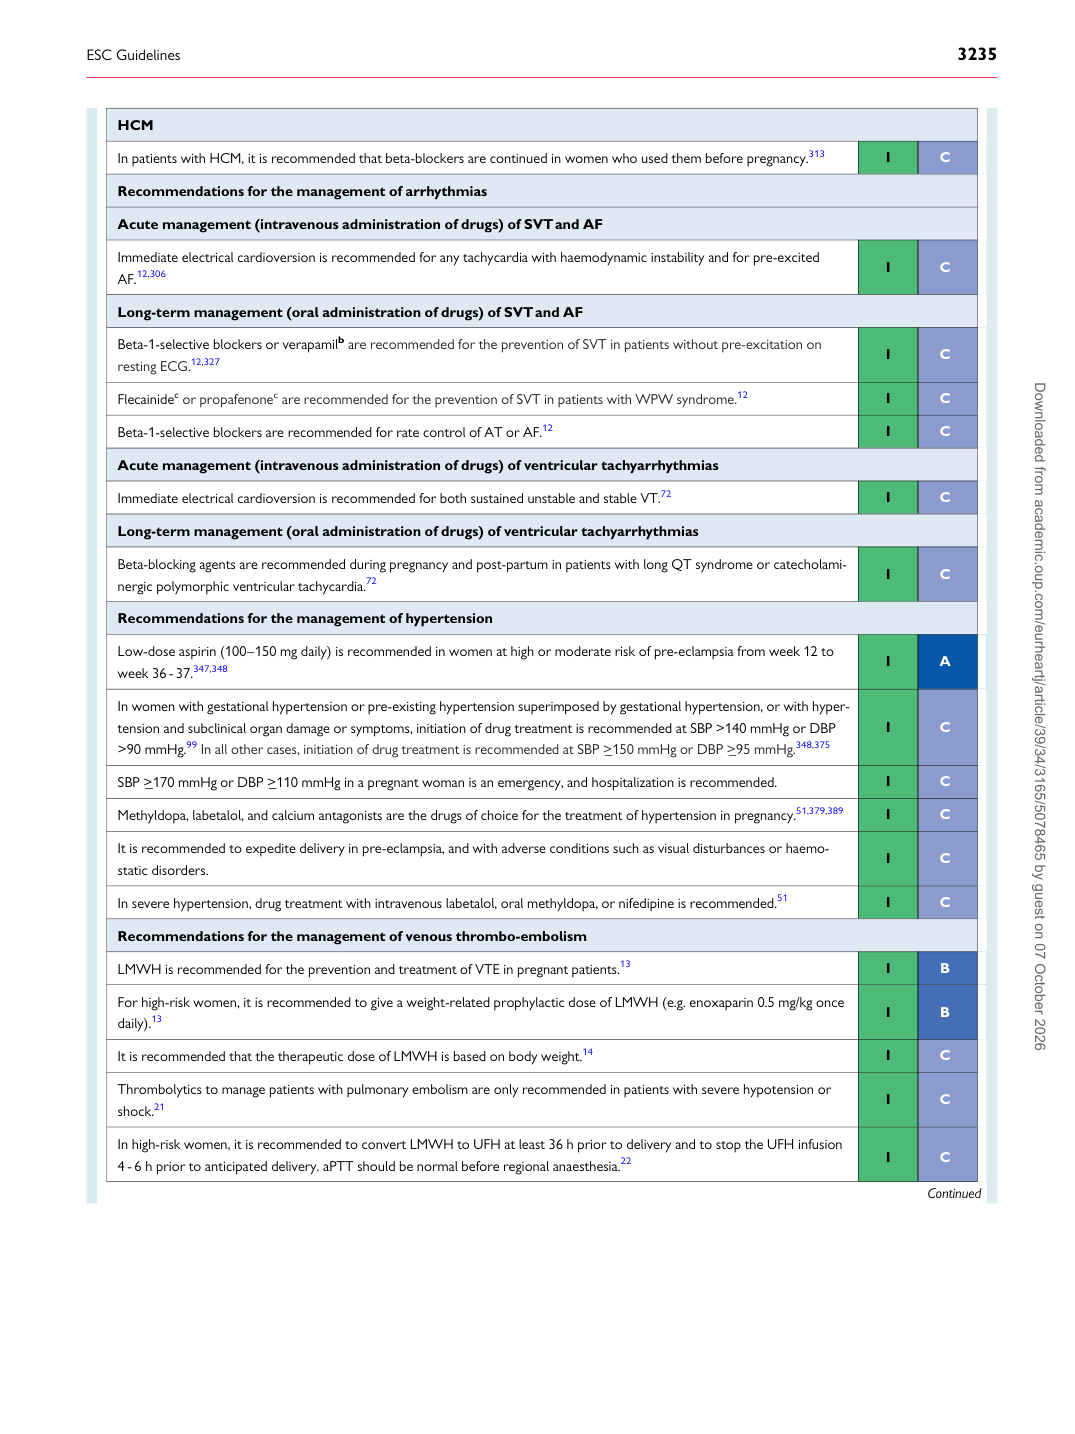
HCM In patients with HCM, it is recommended that beta-blockers are continued in women who used them before pregnancy.313 I C

Recommendations for the management of arrhythmias

Acute management (intravenous administration of drugs) of SVTand AF

Immediate electrical cardioversion is recommended for any tachycardia with haemodynamic instability and for pre-excited AF.12,306 I C

Long-term management (oral administration of drugs) of SVTand AF Beta-1-selective blockers or verapamilb are recommended for the prevention of SVT in patients without pre-excitation on resting ECG.12,327 I C Flecainidec or propafenonec are recommended for the prevention of SVT in patients with WPW syndrome.12 I C Beta-1-selective blockers are recommended for rate control of AT or AF.12 I C

Acute management (intravenous administration of drugs) of ventricular tachyarrhythmias Immediate electrical cardioversion is recommended for both sustained unstable and stable VT.72 I C

Long-term management (oral administration of drugs) of ventricular tachyarrhythmias

Beta-blocking agents are recommended during pregnancy and post-partum in patients with long QT syndrome or catecholaminergic polymorphic ventricular tachycardia.72 I C

Recommendations for the management of hypertension

Low-dose aspirin (100–150 mg daily) is recommended in women at high or moderate risk of pre-eclampsia from week 12 to week 36 - 37.347,348 I A

In women with gestational hypertension or pre-existing hypertension superimposed by gestational hypertension, or with hypertension and subclinical organ damage or symptoms, initiation of drug treatment is recommended at SBP >140 mmHg or DBP >90 mmHg.99 In all other cases, initiation of drug treatment is recommended at SBP >_150 mmHg or DBP >_95 mmHg.348,375 I C

SBP >_170 mmHg or DBP >_110 mmHg in a pregnant woman is an emergency, and hospitalization is recommended. I C Methyldopa, labetalol, and calcium antagonists are the drugs of choice for the treatment of hypertension in pregnancy.51,379,389 I C

It is recommended to expedite delivery in pre-eclampsia, and with adverse conditions such as visual disturbances or haemostatic disorders. I C In severe hypertension, drug treatment with intravenous labetalol, oral methyldopa, or nifedipine is recommended.51 I C

Recommendations for the management of venous thrombo-embolism LMWH is recommended for the prevention and treatment of VTE in pregnant patients.13 I B

For high-risk women, it is recommended to give a weight-related prophylactic dose of LMWH (e.g. enoxaparin 0.5 mg/kg once daily).13 I B It is recommended that the therapeutic dose of LMWH is based on body weight.14 I C

Thrombolytics to manage patients with pulmonary embolism are only recommended in patients with severe hypotension or shock.21 I C

In high-risk women, it is recommended to convert LMWH to UFH at least 36 h prior to delivery and to stop the UFH infusion 4 - 6 h prior to anticipated delivery. aPTT should be normal before regional anaesthesia.22 I C

Continued Downloaded from academic.oup.com/eurheartj/article/39/34/3165/5078465 by guest on 07 October 2026