p.69 抽出テキスト
15 ‘What to do’ and ‘what not to do’ messages from the Guidelines

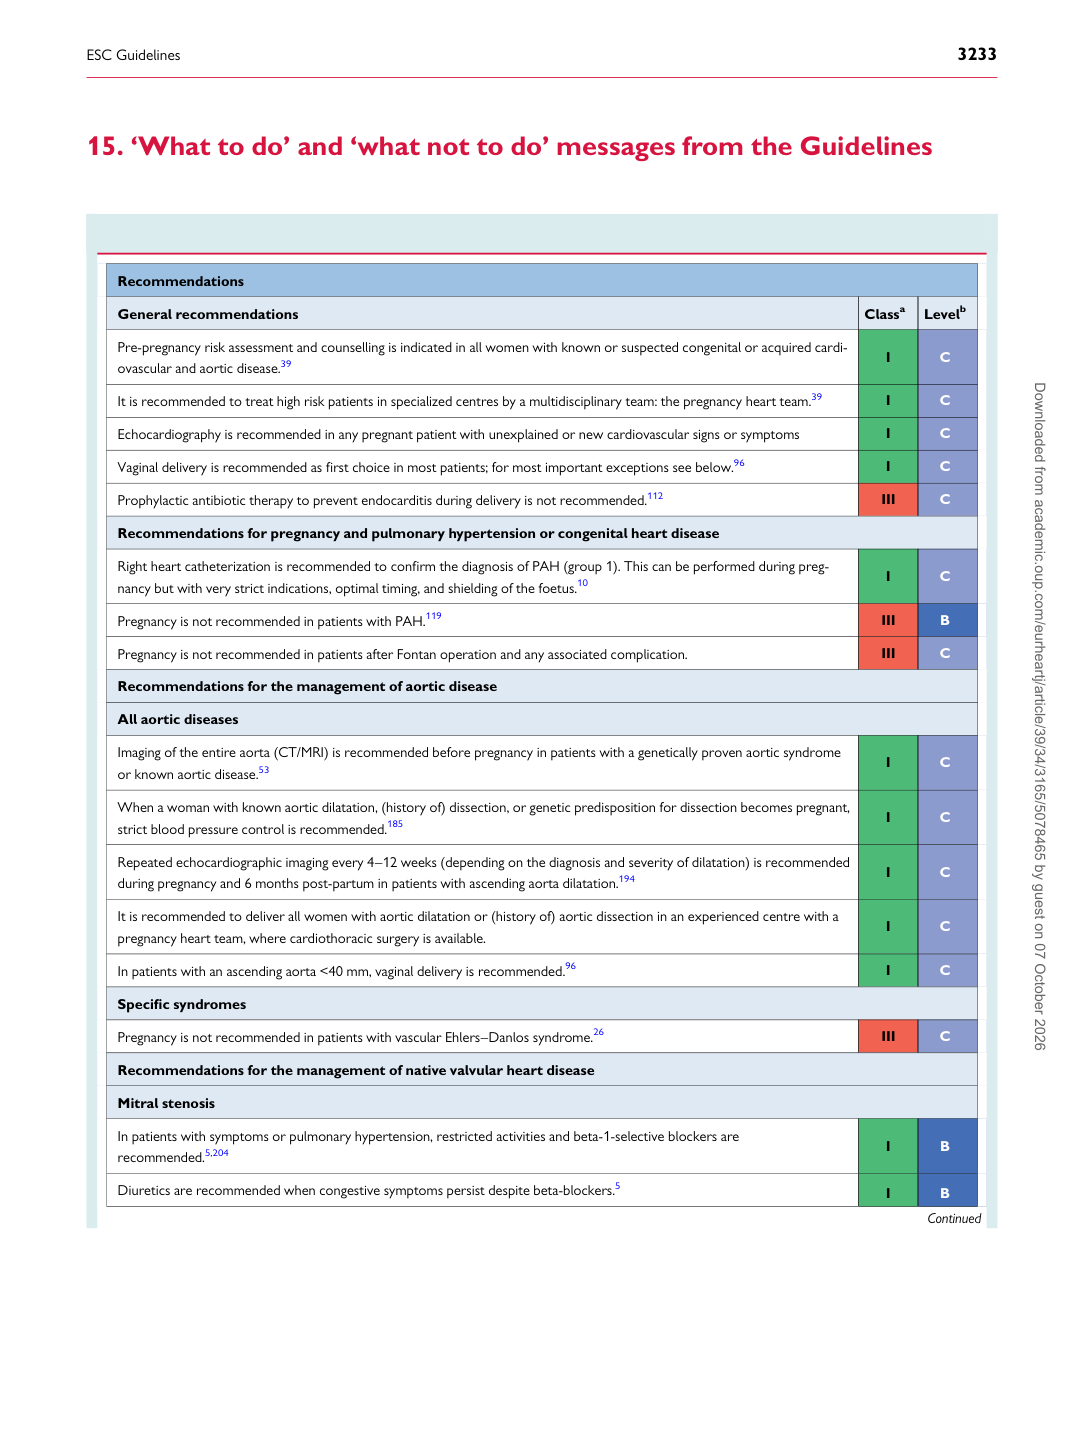
Recommendations General recommendations Classa Levelb

Pre-pregnancy risk assessment and counselling is indicated in all women with known or suspected congenital or acquired cardiovascular and aortic disease.39 I C It is recommended to treat high risk patients in specialized centres by a multidisciplinary team: the pregnancy heart team.39 I C

Echocardiography is recommended in any pregnant patient with unexplained or new cardiovascular signs or symptoms I C Vaginal delivery is recommended as first choice in most patients; for most important exceptions see below.96 I C Prophylactic antibiotic therapy to prevent endocarditis during delivery is not recommended.112 III C

Recommendations for pregnancy and pulmonary hypertension or congenital heart disease

Right heart catheterization is recommended to confirm the diagnosis of PAH (group 1). This can be performed during pregnancy but with very strict indications, optimal timing, and shielding of the foetus.10 I C Pregnancy is not recommended in patients with PAH.119 III B

Pregnancy is not recommended in patients after Fontan operation and any associated complication. III C

Recommendations for the management of aortic disease

All aortic diseases

Imaging of the entire aorta (CT/MRI) is recommended before pregnancy in patients with a genetically proven aortic syndrome or known aortic disease.53 I C

When a woman with known aortic dilatation, (history of) dissection, or genetic predisposition for dissection becomes pregnant, strict blood pressure control is recommended.185 I C

Repeated echocardiographic imaging every 4–12 weeks (depending on the diagnosis and severity of dilatation) is recommended during pregnancy and 6 months post-partum in patients with ascending aorta dilatation.194 I C

It is recommended to deliver all women with aortic dilatation or (history of) aortic dissection in an experienced centre with a pregnancy heart team, where cardiothoracic surgery is available. I C In patients with an ascending aorta <40 mm, vaginal delivery is recommended.96 I C

Specific syndromes Pregnancy is not recommended in patients with vascular Ehlers–Danlos syndrome.26 III C

Recommendations for the management of native valvular heart disease

Mitral stenosis

In patients with symptoms or pulmonary hypertension, restricted activities and beta-1-selective blockers are recommended.5,204 I B Diuretics are recommended when congestive symptoms persist despite beta-blockers.5 I B

Continued Downloaded from academic.oup.com/eurheartj/article/39/34/3165/5078465 by guest on 07 October 2026