p.42 抽出テキスト
9.9 Recommendations

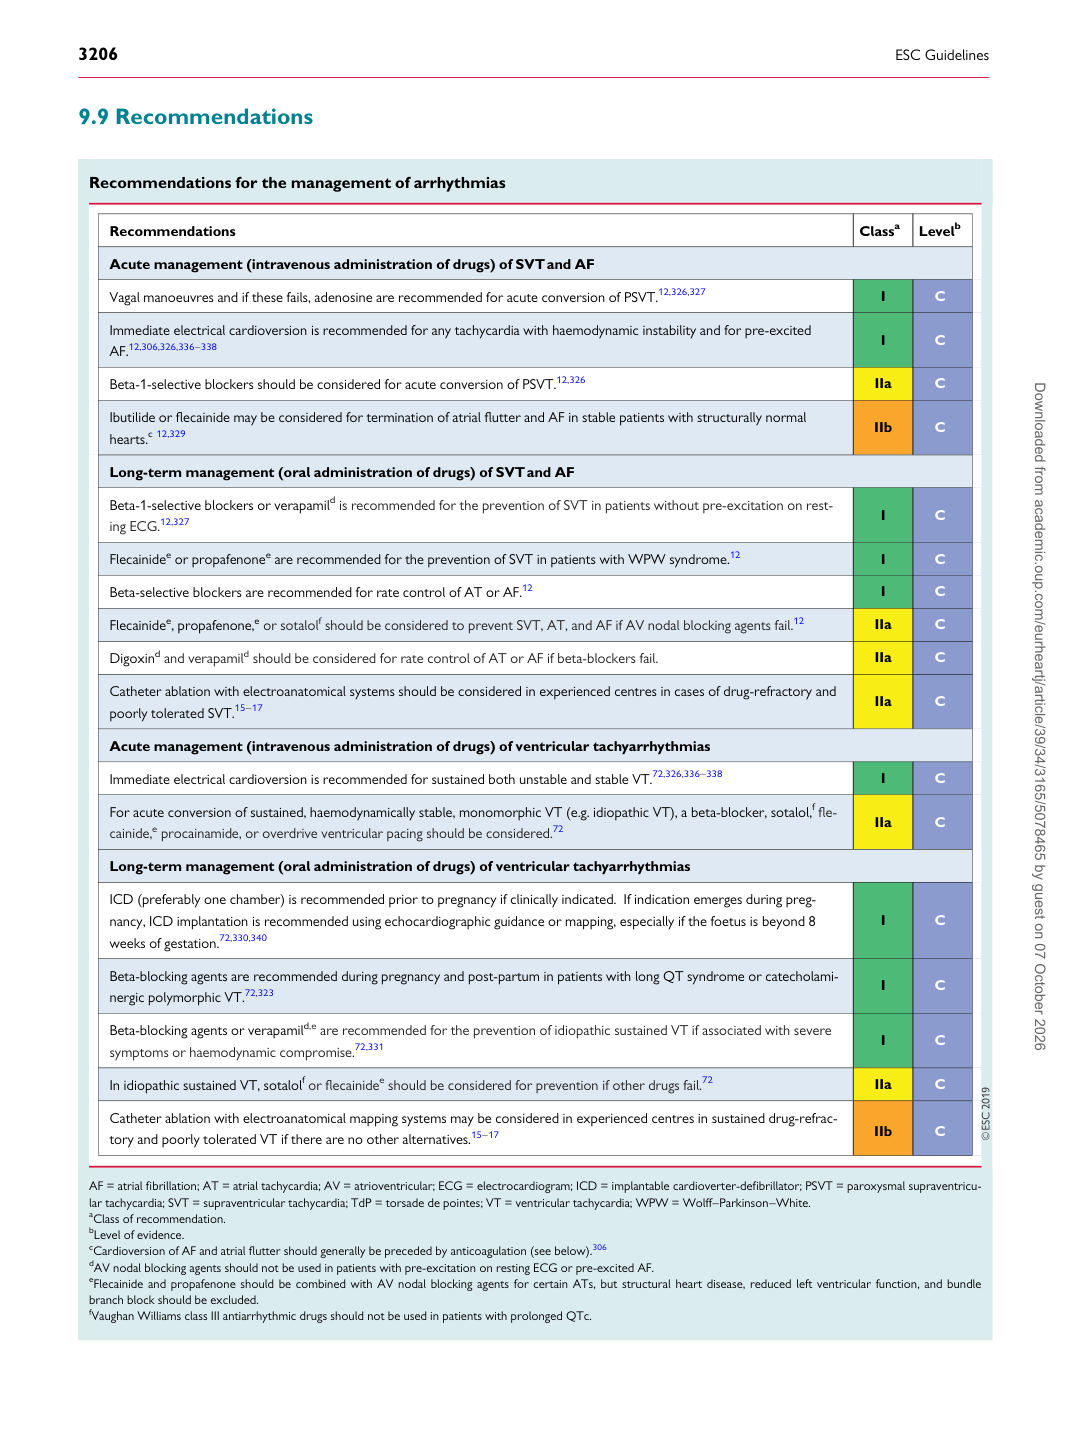
Recommendations for the management of arrhythmias

Recommendations Classa Levelb

Acute management (intravenous administration of drugs) of SVTand AF Vagal manoeuvres and if these fails, adenosine are recommended for acute conversion of PSVT.12,326,327 I C

Immediate electrical cardioversion is recommended for any tachycardia with haemodynamic instability and for pre-excited AF.12,306,326,336–338 I C Beta-1-selective blockers should be considered for acute conversion of PSVT.12,326 IIa C

Ibutilide or flecainide may be considered for termination of atrial flutter and AF in stable patients with structurally normal hearts.c 12,329 IIb C

Long-term management (oral administration of drugs) of SVTand AF Beta-1-selective blockers or verapamild is recommended for the prevention of SVT in patients without pre-excitation on resting ECG.12,327 I C Flecainidee or propafenonee are recommended for the prevention of SVT in patients with WPW syndrome.12 I C Beta-selective blockers are recommended for rate control of AT or AF.12 I C Flecainidee, propafenone,e or sotalolf should be considered to prevent SVT, AT, and AF if AV nodal blocking agents fail.12 IIa C Digoxind and verapamild should be considered for rate control of AT or AF if beta-blockers fail. IIa C

Catheter ablation with electroanatomical systems should be considered in experienced centres in cases of drug-refractory and poorly tolerated SVT.15–17 IIa C

Acute management (intravenous administration of drugs) of ventricular tachyarrhythmias Immediate electrical cardioversion is recommended for sustained both unstable and stable VT.72,326,336–338 I C For acute conversion of sustained, haemodynamically stable, monomorphic VT (e.g. idiopathic VT), a beta-blocker, sotalol,f flecainide,e procainamide, or overdrive ventricular pacing should be considered.72 IIa C

Long-term management (oral administration of drugs) of ventricular tachyarrhythmias

ICD (preferably one chamber) is recommended prior to pregnancy if clinically indicated. If indication emerges during pregnancy, ICD implantation is recommended using echocardiographic guidance or mapping, especially if the foetus is beyond 8 weeks of gestation.72,330,340 I C

Beta-blocking agents are recommended during pregnancy and post-partum in patients with long QT syndrome or catecholaminergic polymorphic VT.72,323 I C Beta-blocking agents or verapamild,e are recommended for the prevention of idiopathic sustained VT if associated with severe symptoms or haemodynamic compromise.72,331 I C In idiopathic sustained VT, sotalolf or flecainidee should be considered for prevention if other drugs fail.72 IIa C

Catheter ablation with electroanatomical mapping systems may be considered in experienced centres in sustained drug-refractory and poorly tolerated VT if there are no other alternatives.15–17 IIb C

AF = atrial fibrillation; AT = atrial tachycardia; AV = atrioventricular; ECG = electrocardiogram; ICD = implantable cardioverter-defibrillator; PSVT = paroxysmal supraventricular tachycardia; SVT = supraventricular tachycardia; TdP = torsade de pointes; VT = ventricular tachycardia; WPW = Wolff–Parkinson–White. aClass of recommendation. bLevel of evidence. cCardioversion of AF and atrial flutter should generally be preceded by anticoagulation (see below).306 dAV nodal blocking agents should not be used in patients with pre-excitation on resting ECG or pre-excited AF. eFlecainide and propafenone should be combined with AV nodal blocking agents for certain ATs, but structural heart disease, reduced left ventricular function, and bundle branch block should be excluded. fVaughan Williams class III antiarrhythmic drugs should not be used in patients with prolonged QTc. Downloaded from academic.oup.com/eurheartj/article/39/34/3165/5078465 by guest on 07 October 2026