p.38 抽出テキスト
...................... 8.4.2 Delivery Low-risk cases may have a spontaneous labour and vaginal delivery. Caesarean section should be considered in patients with severe LV outflow tract obstruction, pre-term labour while on OACs, or severe HF.9 Epidural and spinal anaesthesia must be applied cautiously, especially with severe LV outflow tract obstruction, because of potential hypovolaemia, and single-shot spinal anaesthesia avoided. During delivery, monitoring of heart rate and rhythm should be considered in patients with a high-risk of developing arrhythmias. Oxytocin should be given as a slow infusion and any i.v. fluids given judiciously.9,317

8.5 Recommendations

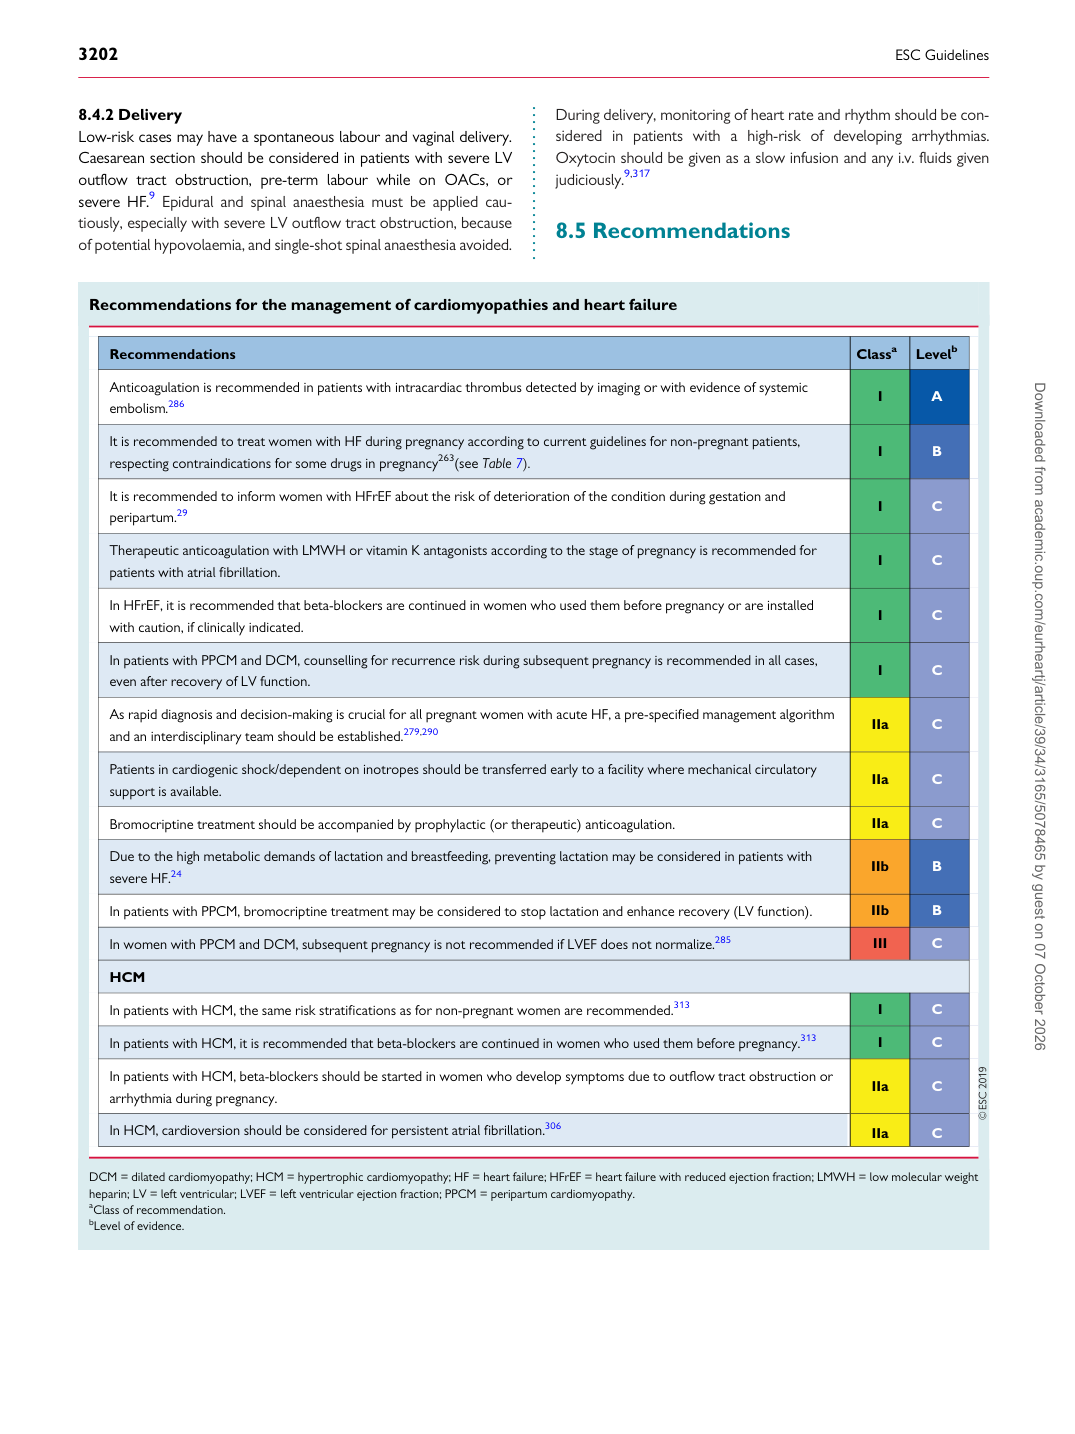
Recommendations for the management of cardiomyopathies and heart failure

Recommendations Classa Levelb

Anticoagulation is recommended in patients with intracardiac thrombus detected by imaging or with evidence of systemic embolism.286 I A

It is recommended to treat women with HF during pregnancy according to current guidelines for non-pregnant patients, respecting contraindications for some drugs in pregnancy263(see Table 7). I B

It is recommended to inform women with HFrEF about the risk of deterioration of the condition during gestation and peripartum.29 I C

Therapeutic anticoagulation with LMWH or vitamin K antagonists according to the stage of pregnancy is recommended for patients with atrial fibrillation. I C

In HFrEF, it is recommended that beta-blockers are continued in women who used them before pregnancy or are installed with caution, if clinically indicated. I C

In patients with PPCM and DCM, counselling for recurrence risk during subsequent pregnancy is recommended in all cases, even after recovery of LV function. I C

As rapid diagnosis and decision-making is crucial for all pregnant women with acute HF, a pre-specified management algorithm and an interdisciplinary team should be established.279,290 IIa C

Patients in cardiogenic shock/dependent on inotropes should be transferred early to a facility where mechanical circulatory support is available. IIa C

Bromocriptine treatment should be accompanied by prophylactic (or therapeutic) anticoagulation. IIa C

Due to the high metabolic demands of lactation and breastfeeding, preventing lactation may be considered in patients with severe HF.24 IIb B

In patients with PPCM, bromocriptine treatment may be considered to stop lactation and enhance recovery (LV function). IIb B In women with PPCM and DCM, subsequent pregnancy is not recommended if LVEF does not normalize.285 III C

HCM In patients with HCM, the same risk stratifications as for non-pregnant women are recommended.313 I C In patients with HCM, it is recommended that beta-blockers are continued in women who used them before pregnancy.313 I C

In patients with HCM, beta-blockers should be started in women who develop symptoms due to outflow tract obstruction or arrhythmia during pregnancy. IIa C In HCM, cardioversion should be considered for persistent atrial fibrillation.306 IIa C

DCM = dilated cardiomyopathy; HCM = hypertrophic cardiomyopathy; HF = heart failure; HFrEF = heart failure with reduced ejection fraction; LMWH = low molecular weight heparin; LV = left ventricular; LVEF = left ventricular ejection fraction; PPCM = peripartum cardiomyopathy. aClass of recommendation. bLevel of evidence. Downloaded from academic.oup.com/eurheartj/article/39/34/3165/5078465 by guest on 07 October 2026