p.25 抽出テキスト
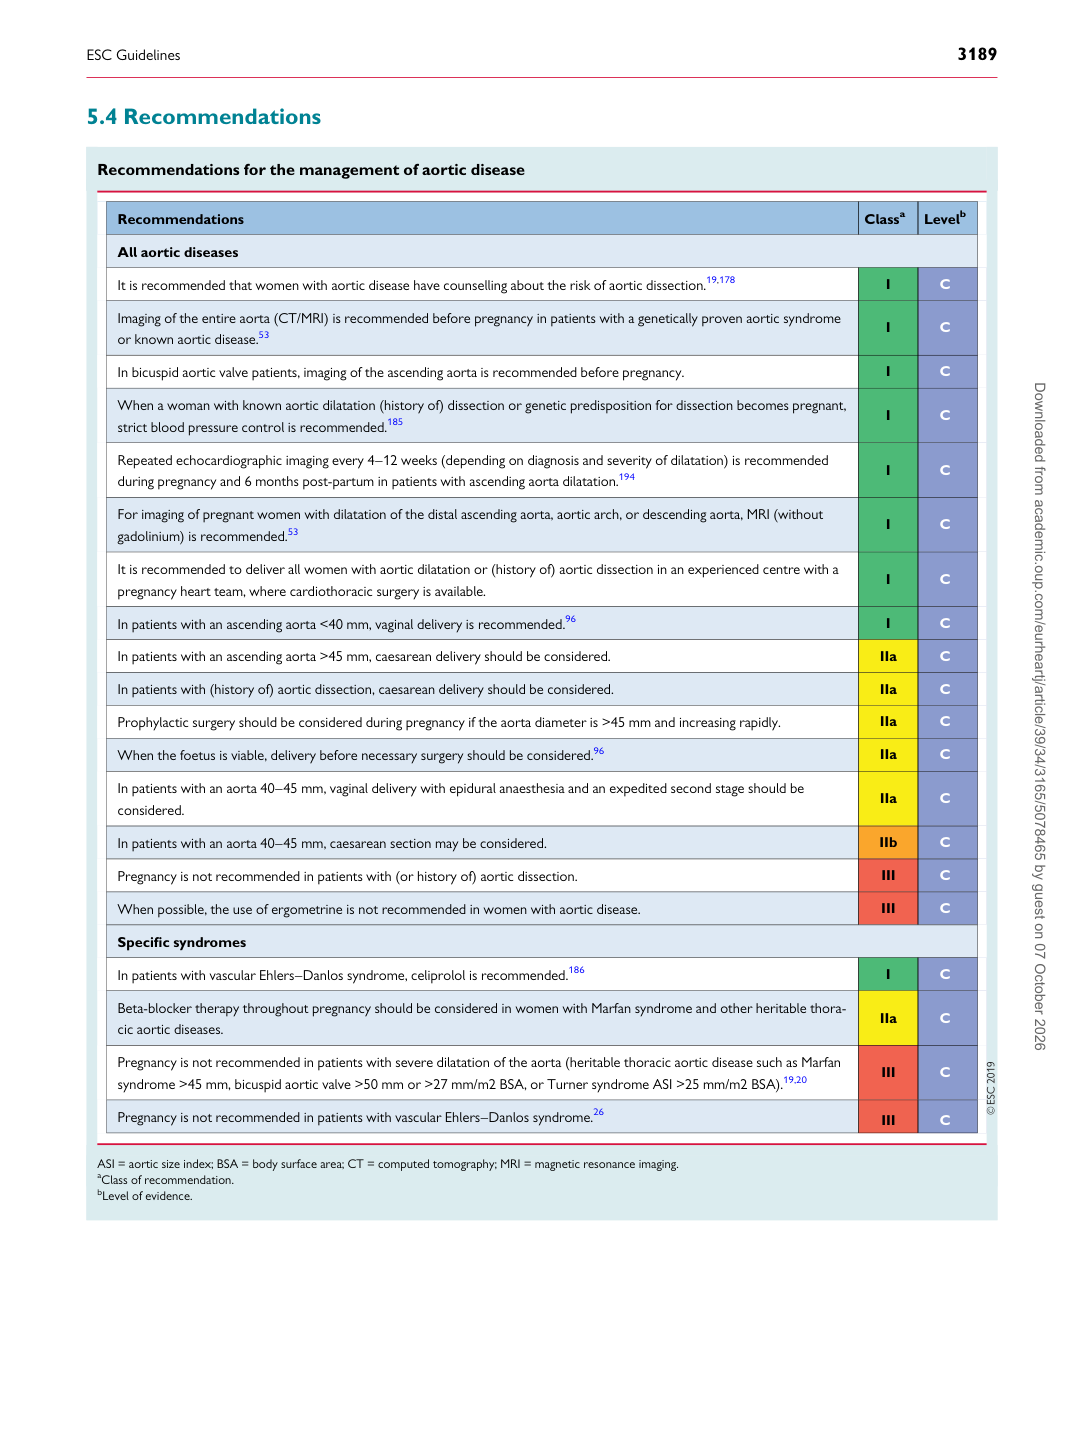
5.4 Recommendations

Recommendations for the management of aortic disease

Recommendations Classa Levelb

All aortic diseases It is recommended that women with aortic disease have counselling about the risk of aortic dissection.19,178 I C

Imaging of the entire aorta (CT/MRI) is recommended before pregnancy in patients with a genetically proven aortic syndrome or known aortic disease.53 I C

In bicuspid aortic valve patients, imaging of the ascending aorta is recommended before pregnancy. I C

When a woman with known aortic dilatation (history of) dissection or genetic predisposition for dissection becomes pregnant, strict blood pressure control is recommended.185 I C

Repeated echocardiographic imaging every 4–12 weeks (depending on diagnosis and severity of dilatation) is recommended during pregnancy and 6 months post-partum in patients with ascending aorta dilatation.194 I C

For imaging of pregnant women with dilatation of the distal ascending aorta, aortic arch, or descending aorta, MRI (without gadolinium) is recommended.53 I C

It is recommended to deliver all women with aortic dilatation or (history of) aortic dissection in an experienced centre with a pregnancy heart team, where cardiothoracic surgery is available. I C In patients with an ascending aorta <40 mm, vaginal delivery is recommended.96 I C

In patients with an ascending aorta >45 mm, caesarean delivery should be considered. IIa C

In patients with (history of) aortic dissection, caesarean delivery should be considered. IIa C

Prophylactic surgery should be considered during pregnancy if the aorta diameter is >45 mm and increasing rapidly. IIa C When the foetus is viable, delivery before necessary surgery should be considered.96 IIa C

In patients with an aorta 40–45 mm, vaginal delivery with epidural anaesthesia and an expedited second stage should be considered. IIa C

In patients with an aorta 40–45 mm, caesarean section may be considered. IIb C

Pregnancy is not recommended in patients with (or history of) aortic dissection. III C

When possible, the use of ergometrine is not recommended in women with aortic disease. III C

Specific syndromes In patients with vascular Ehlers–Danlos syndrome, celiprolol is recommended.186 I C

Beta-blocker therapy throughout pregnancy should be considered in women with Marfan syndrome and other heritable thoracic aortic diseases. IIa C

Pregnancy is not recommended in patients with severe dilatation of the aorta (heritable thoracic aortic disease such as Marfan syndrome >45 mm, bicuspid aortic valve >50 mm or >27 mm/m2 BSA, or Turner syndrome ASI >25 mm/m2 BSA).19,20 III C Pregnancy is not recommended in patients with vascular Ehlers–Danlos syndrome.26 III C

ASI = aortic size index; BSA = body surface area; CT = computed tomography; MRI = magnetic resonance imaging. aClass of recommendation. bLevel of evidence. Downloaded from academic.oup.com/eurheartj/article/39/34/3165/5078465 by guest on 07 October 2026